DraftNot yet reviewed by the clinical team · Last edited 14 October 2026
Vertebroplasty and kyphoplasty
When a weak bone in your spine cracks and squashes down, it can cause severe back pain. The doctor fills the broken bone with medical bone cement through a hollow needle in your back, with no surgical cut and no stitches.
The short version
- Osteoporosis can make a bone in your spine so weak that it cracks and squashes down, which causes sudden back pain.
- In vertebroplasty, the doctor puts a hollow needle through a tiny nick in your back and fills the broken bone with bone cement.
- Kyphoplasty adds one step first: a small balloon makes a space inside the bone, and then the space is filled with cement.
- The cement sets hard within about 20 minutes. Many people go home the same day and feel less pain within days, but it does not help everyone.
What it treats
Your spine is a stack of bones
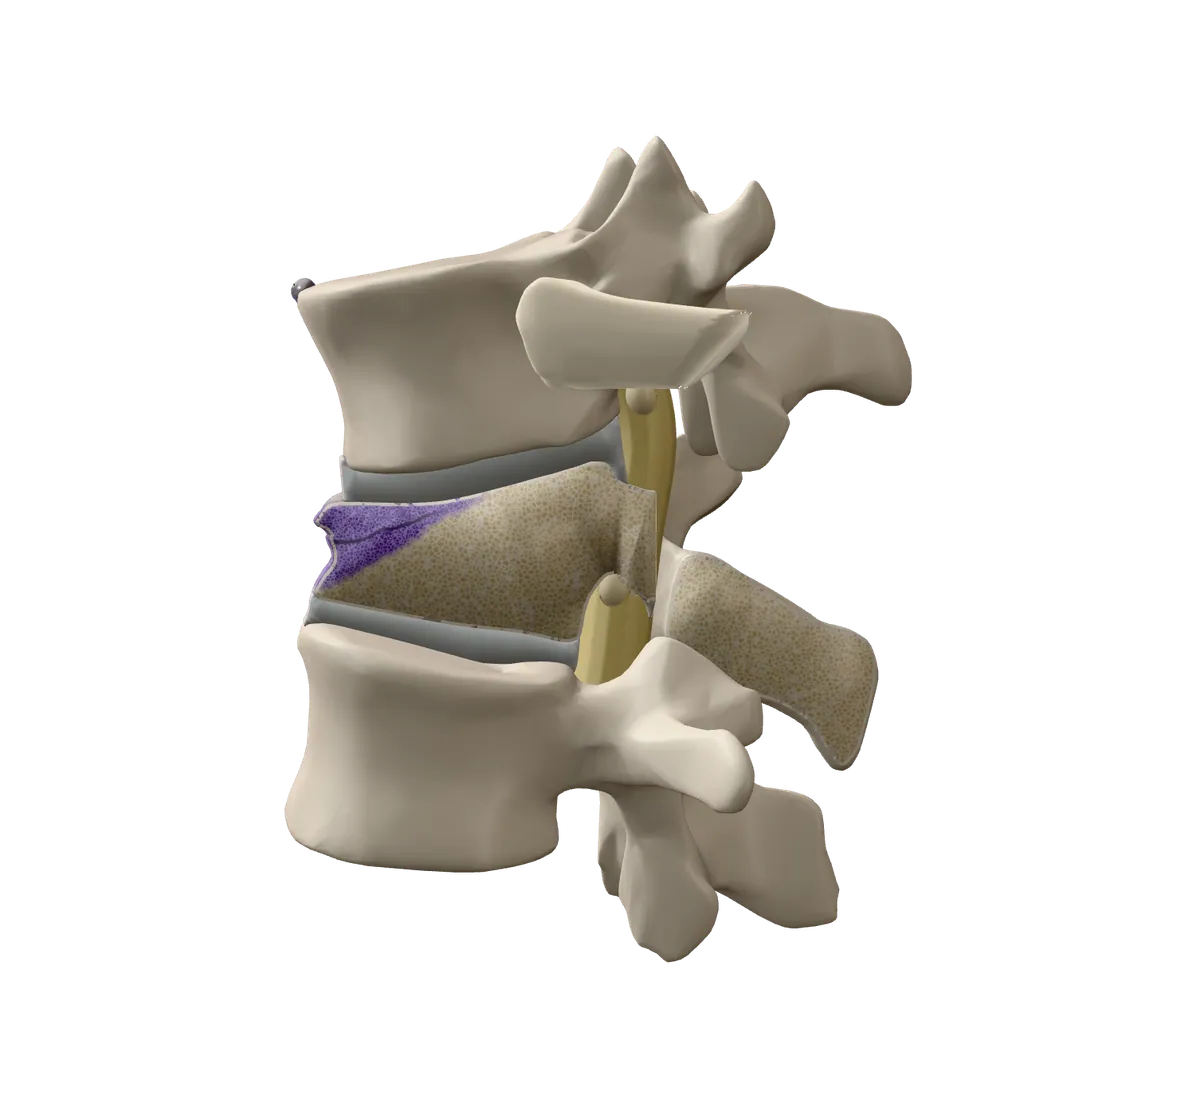
Your spine is made of bones called vertebrae, stacked one on top of another. Each one has a thick, round front part that carries your weight. Soft discs sit between them like cushions.
Behind the bones is a tunnel. It holds your spinal cord and the nerves that run to your body and legs.
Weak bones can crack and squash down
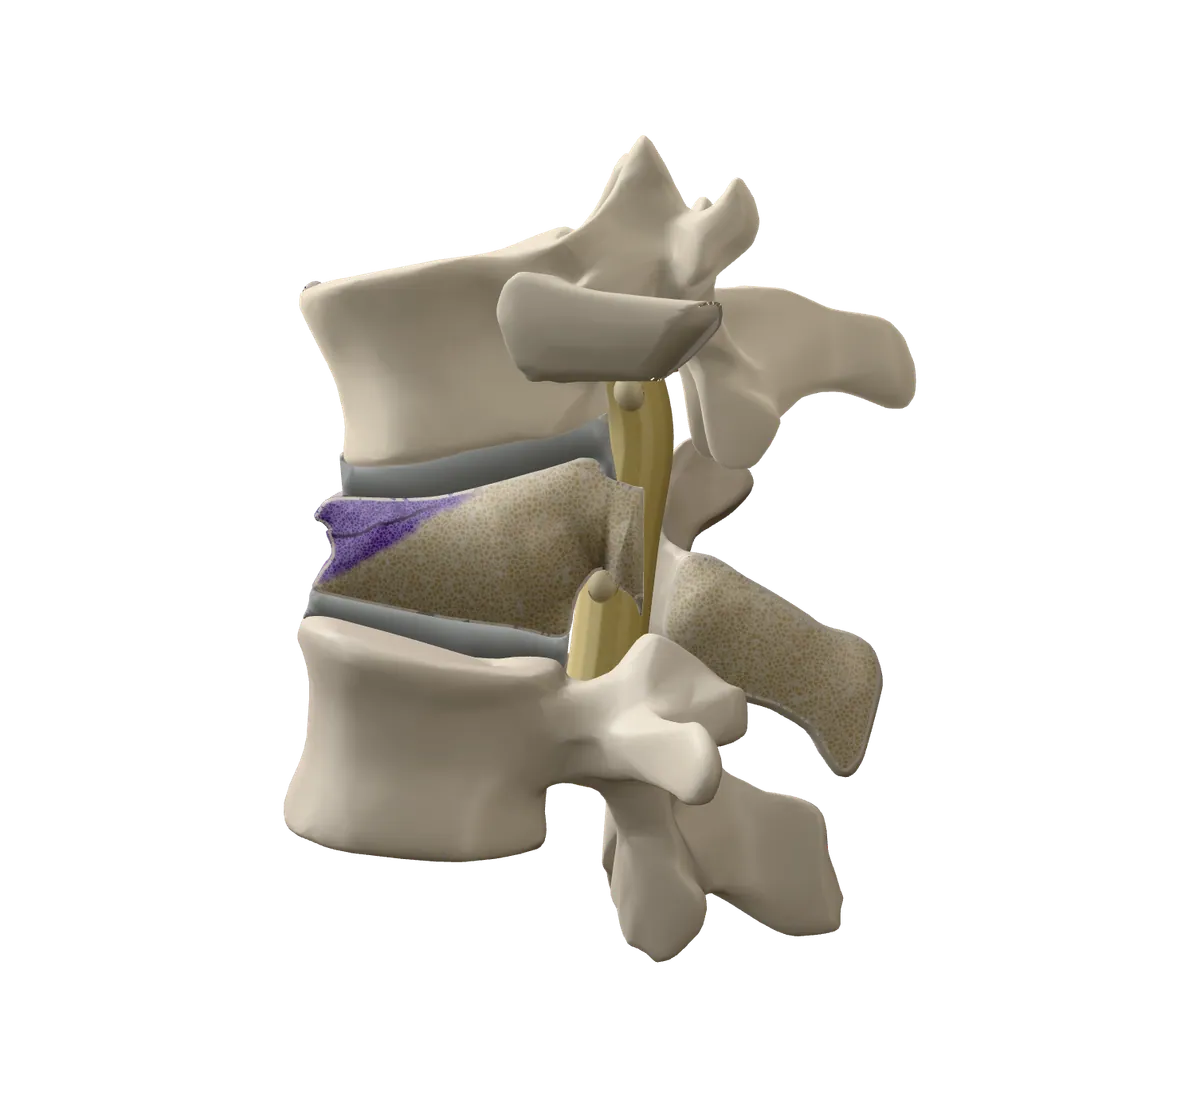
Osteoporosis makes bones thin and weak. A weak vertebra can crack from a small strain, like a sneeze or getting out of a car. The front of the bone squashes down into a wedge. This is called a compression fracture.
It often causes sudden back pain that is worse when you move and better when you rest. Some people lose height or start to stoop forward.
Good to know. Less often, a fracture like this comes from an injury or from cancer in the bone.
How it works
Bone cement works like a cast inside the bone
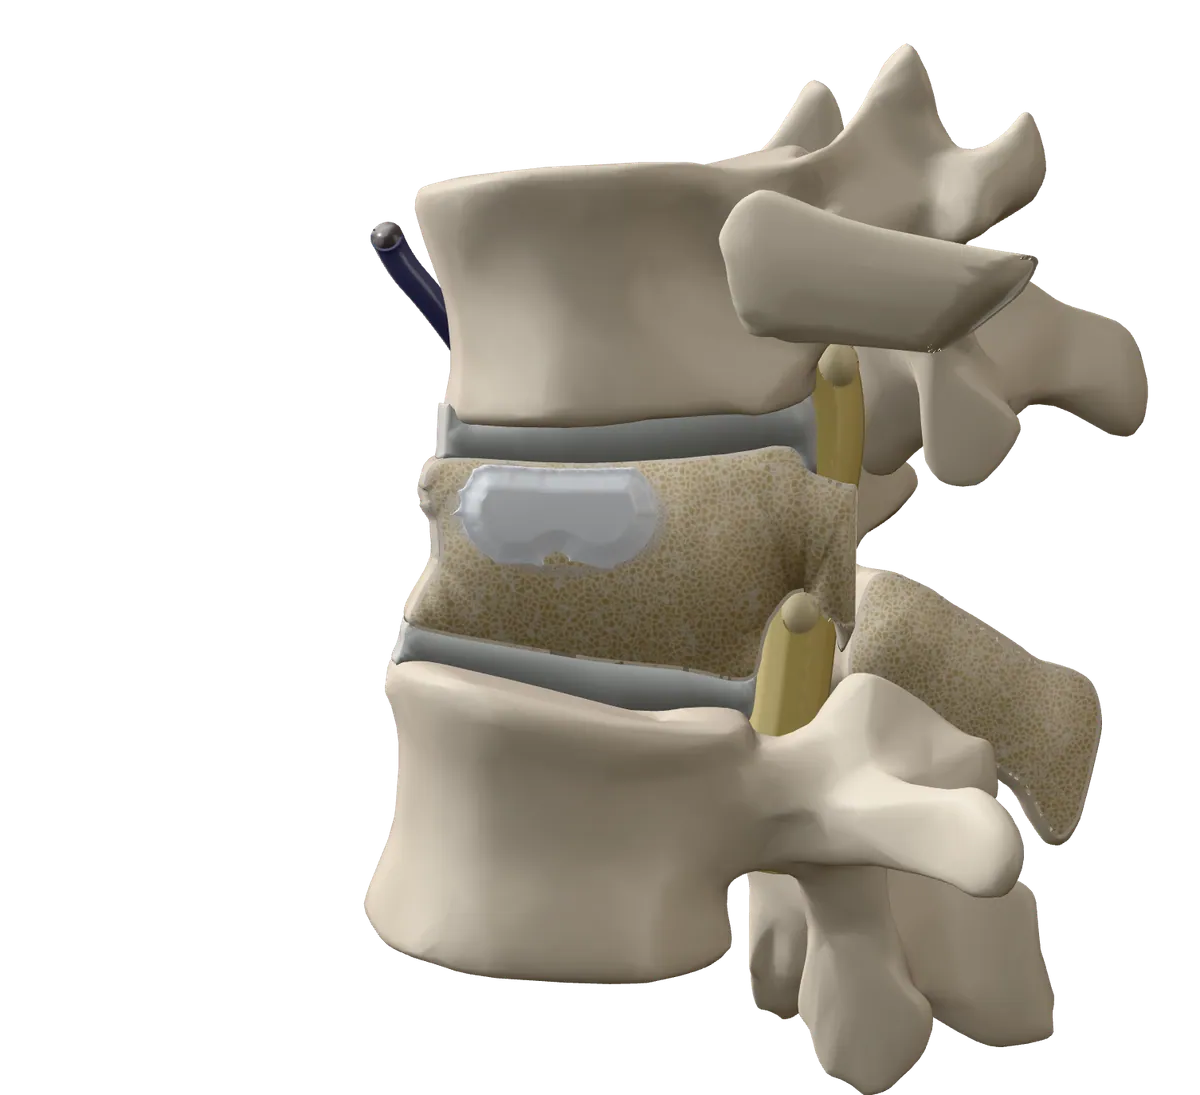
The treatment fills the broken bone with medical bone cement. It goes in as a thick paste, like toothpaste, and sets hard within about 20 minutes. It works like a cast on the inside, holding the broken pieces still.
There are two ways to do it. In vertebroplasty, the cement goes straight into the bone. Kyphoplasty adds one step first: a small balloon is blown up inside the bone to make a space and lift it a little. Then that space is filled with cement.
Is it for you
It is for a new break that stays very painful
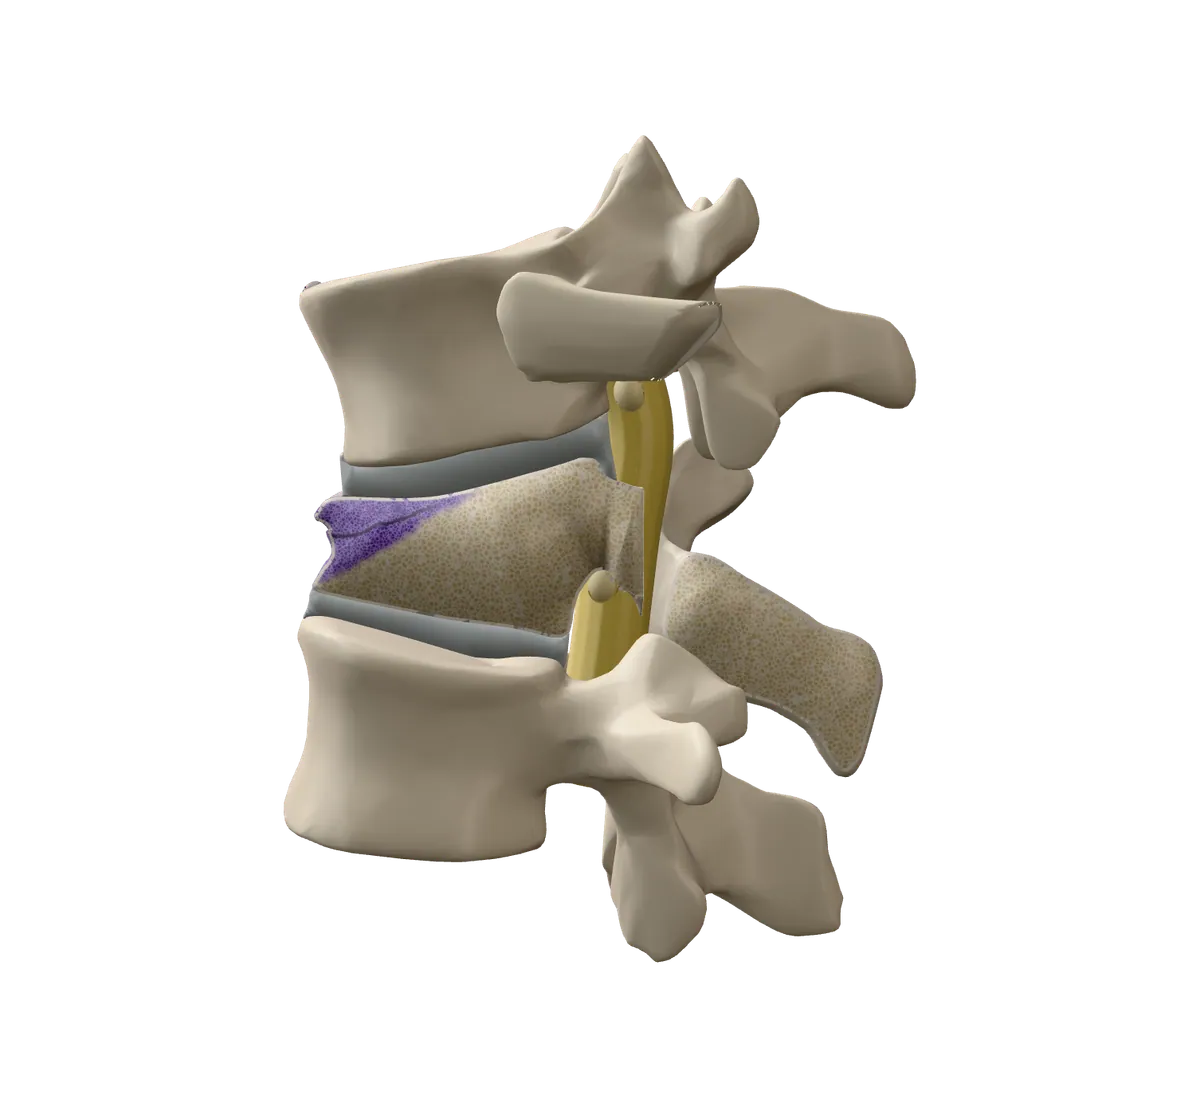
Many of these fractures heal on their own in about 3 months. Rest, pain medicine and sometimes a back brace usually come first. This treatment is offered when the pain stays severe anyway, or when pain medicine causes problems.
It works best on a break that is new and not yet healed, ideally within about 8 weeks. An MRI scan (a detailed scan that uses a strong magnet) shows whether the break is still fresh.
Good to know. It does not help a fracture that has already healed, or back pain from a slipped disc or arthritis.
The procedure
Getting ready
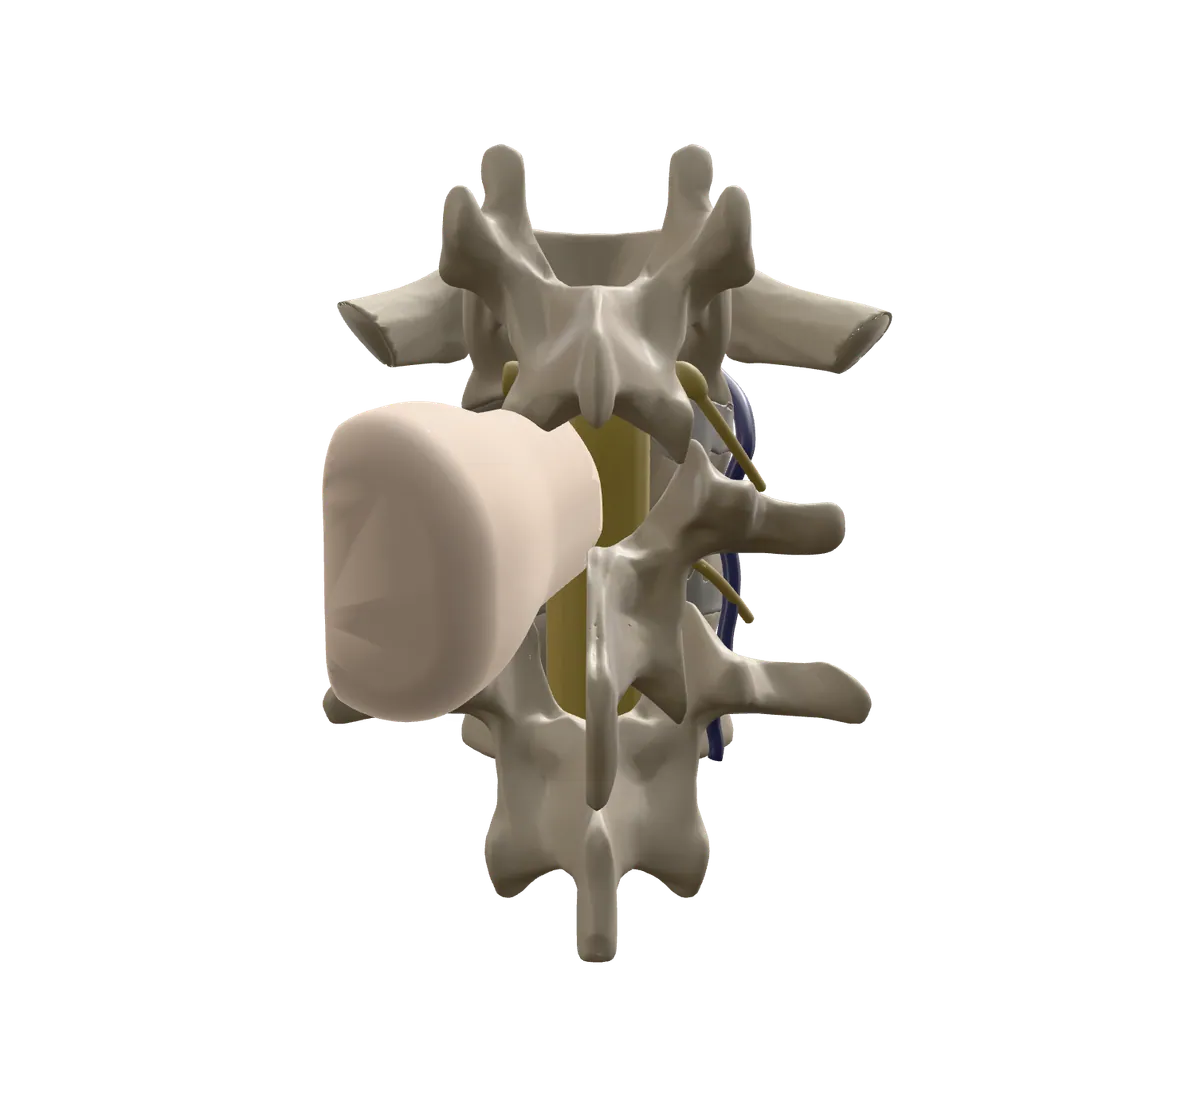
At the hospital, a nurse puts a small tube called an IV in your hand or arm. You lie face down on an X-ray table. Medicine through the IV makes you drowsy and relaxed. Some people have a general anesthetic and sleep through it.
Good to know. You will be told when to stop eating and drinking. You may need to stop blood thinners for several days before, but only if your team tells you to. Plan for an adult to drive you home.
A hollow needle goes into the broken bone
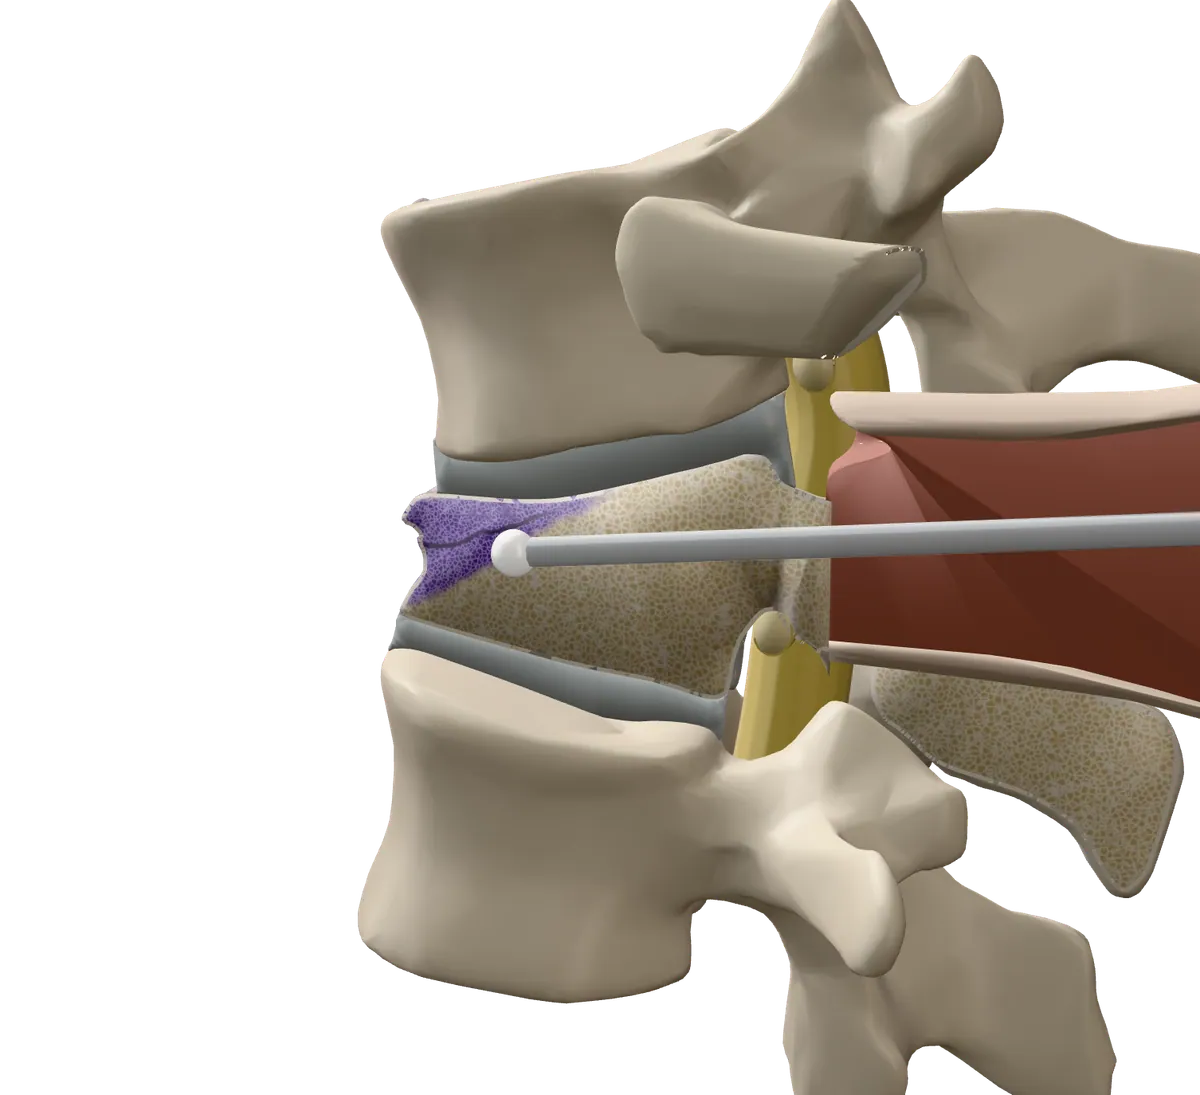
The skin on your back is cleaned and numbed. The doctor makes a tiny nick in the skin. It will not need stitches.
Watching a live X-ray screen, the doctor guides a hollow needle through the back muscles and into the broken bone. It usually passes through a short bridge of bone at the back, called the pedicle. Tell the team if anything hurts.
Kyphoplasty only: a balloon makes room
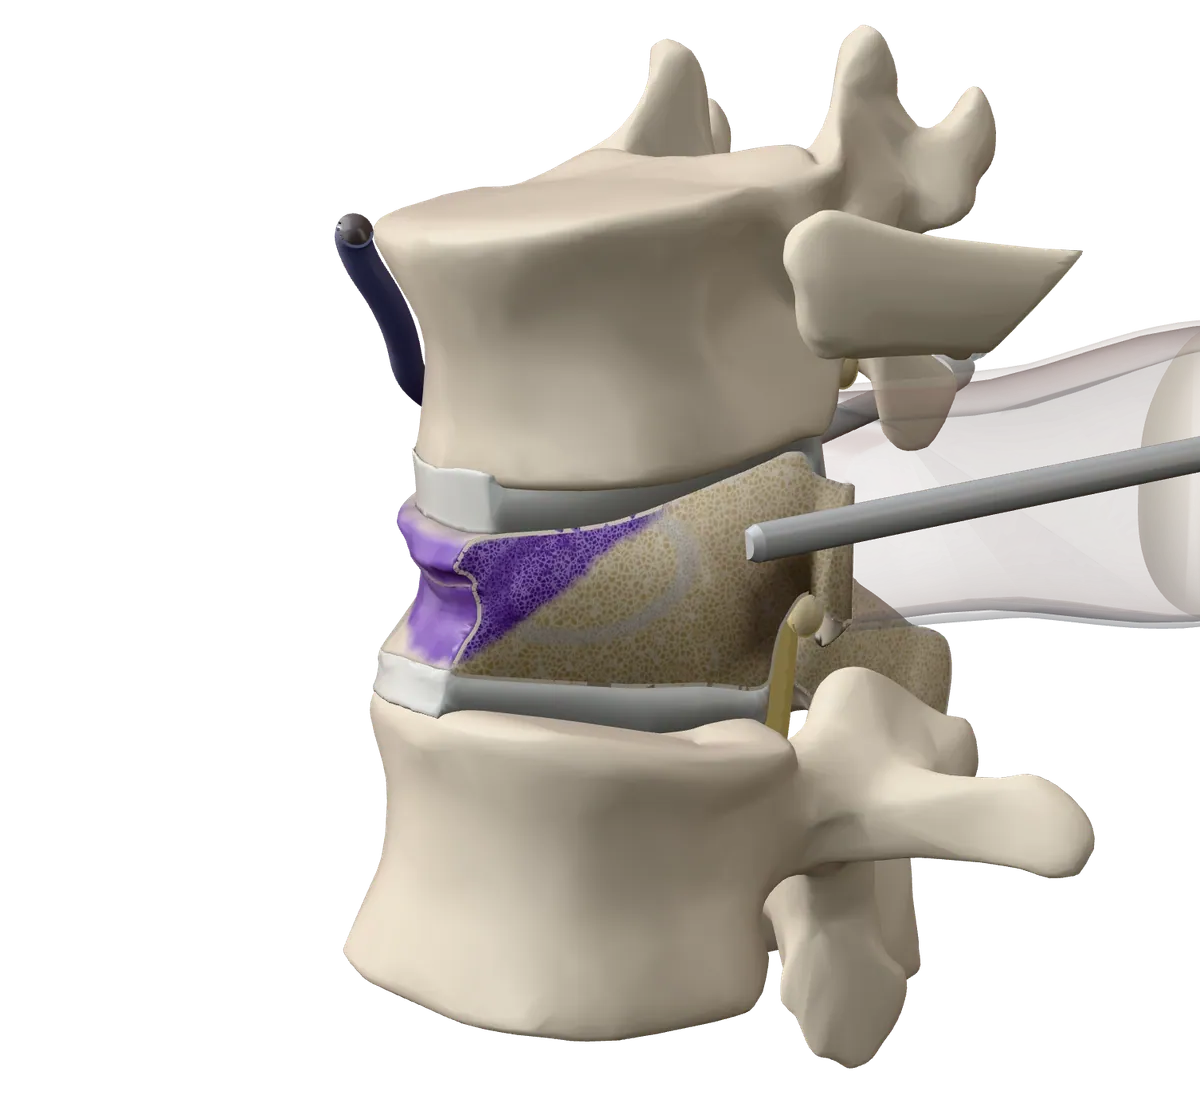
In kyphoplasty, a small balloon goes in through the needle. It is filled with a liquid that shows up on X-ray, so the doctor can watch it grow. Often there is one balloon on each side.
The balloon pushes the crushed bone aside to make a space, and it may lift the bone part of the way back up. Then the balloon is let down and taken out. In vertebroplasty, this step is skipped.
Cement fills the bone
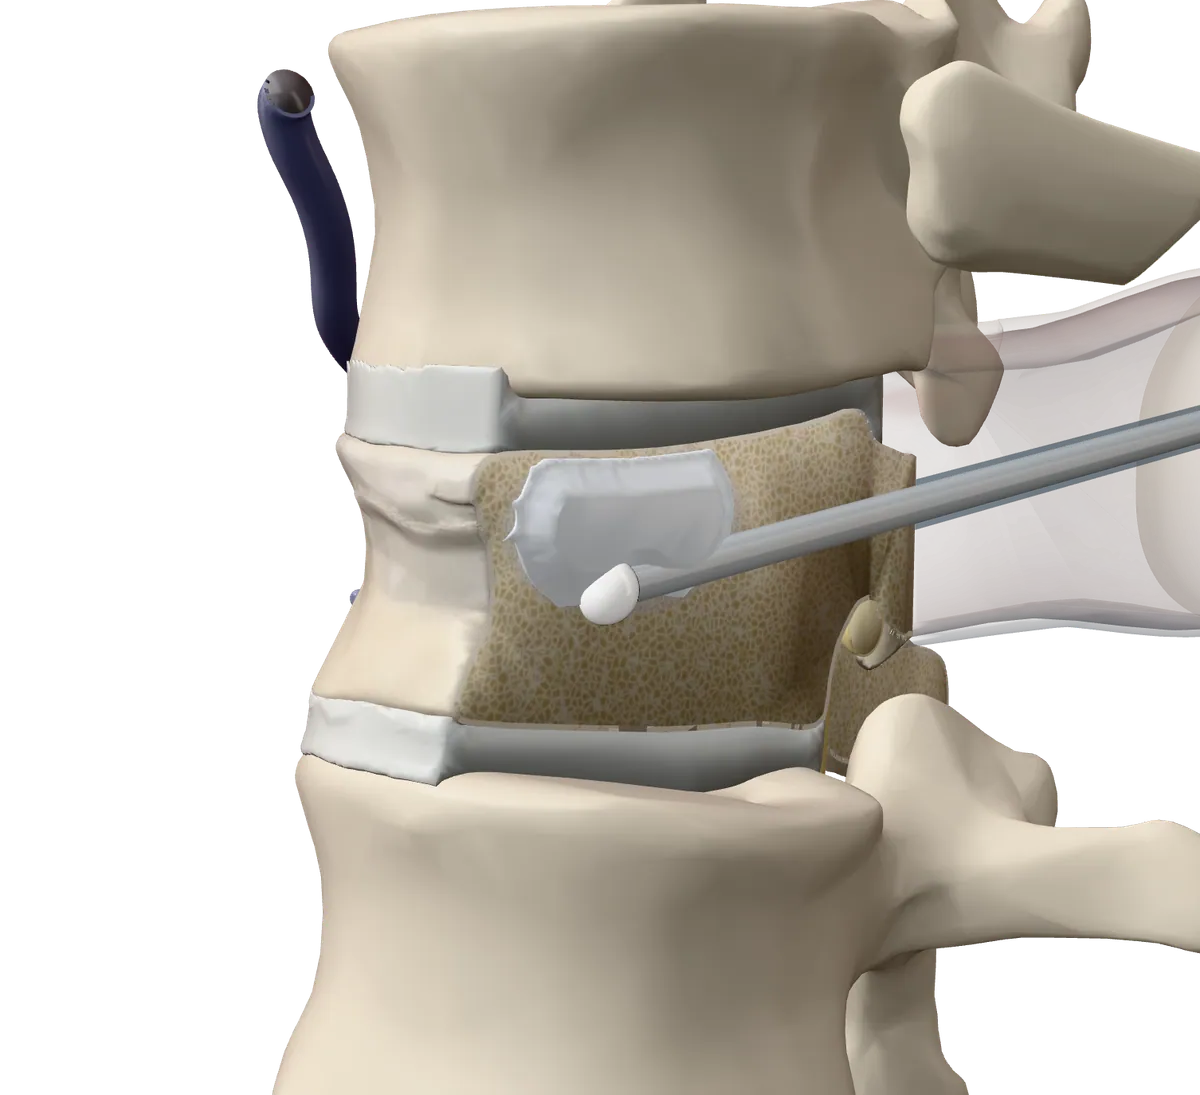
The cement is mixed into a thick paste and pushed through the needle. The doctor watches it on X-ray the whole time, to keep it where it should be.
In vertebroplasty, the cement spreads through the spongy inside of the bone. In kyphoplasty, it fills the space the balloon made. Either way, it sets hard within about 20 minutes.
The needle comes out
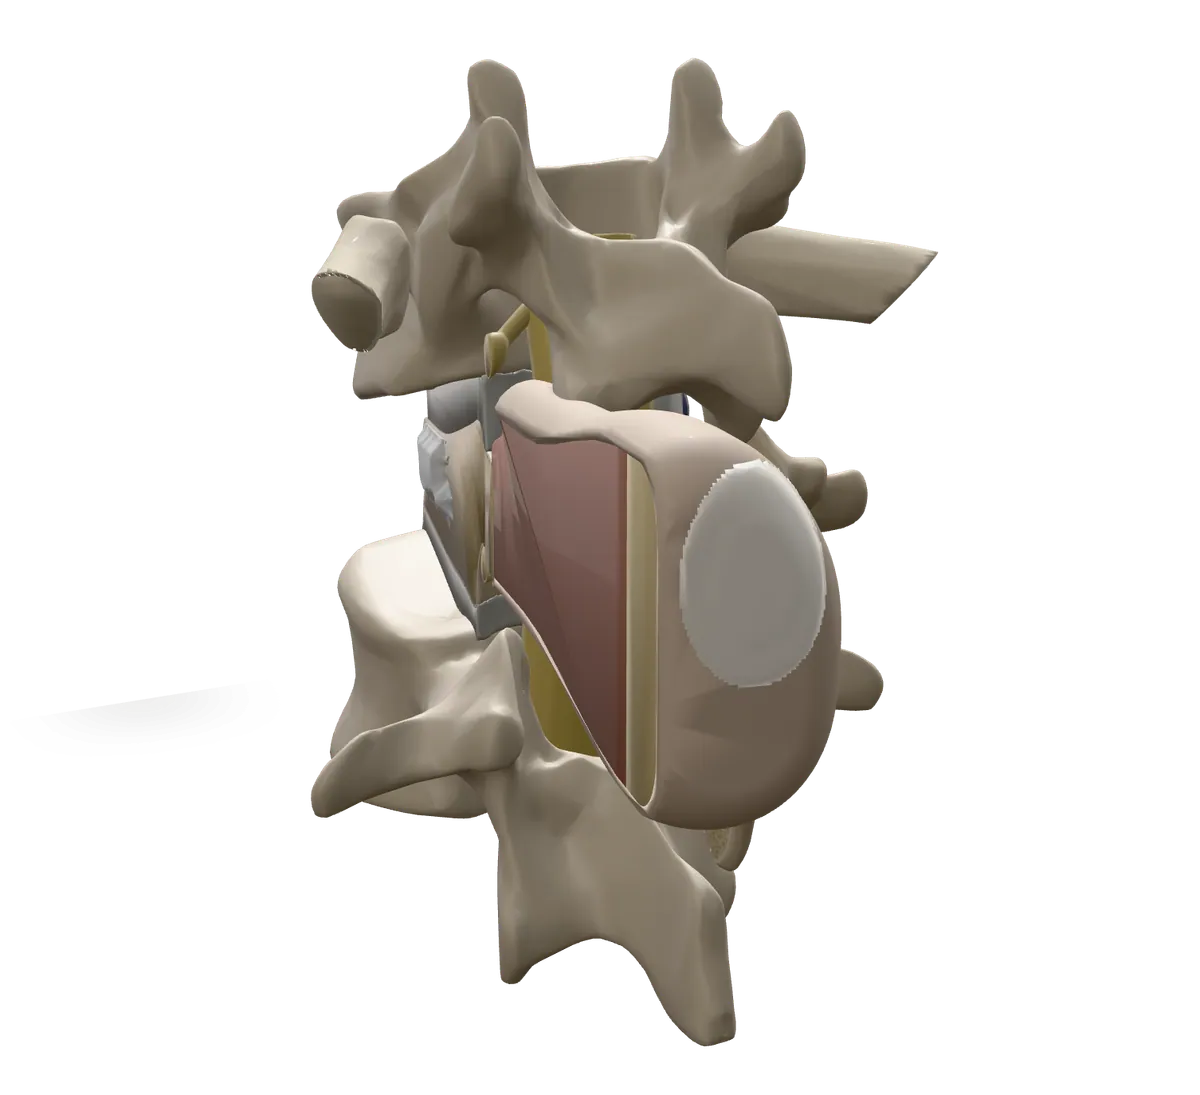
When the cement is in place, the needle is taken out. The team presses on the spot to stop any bleeding and puts on a bandage. There are no stitches.
Good to know. For one bone, the procedure usually takes under an hour. It takes longer if more than one bone is treated.
Afterwards
Resting, then home
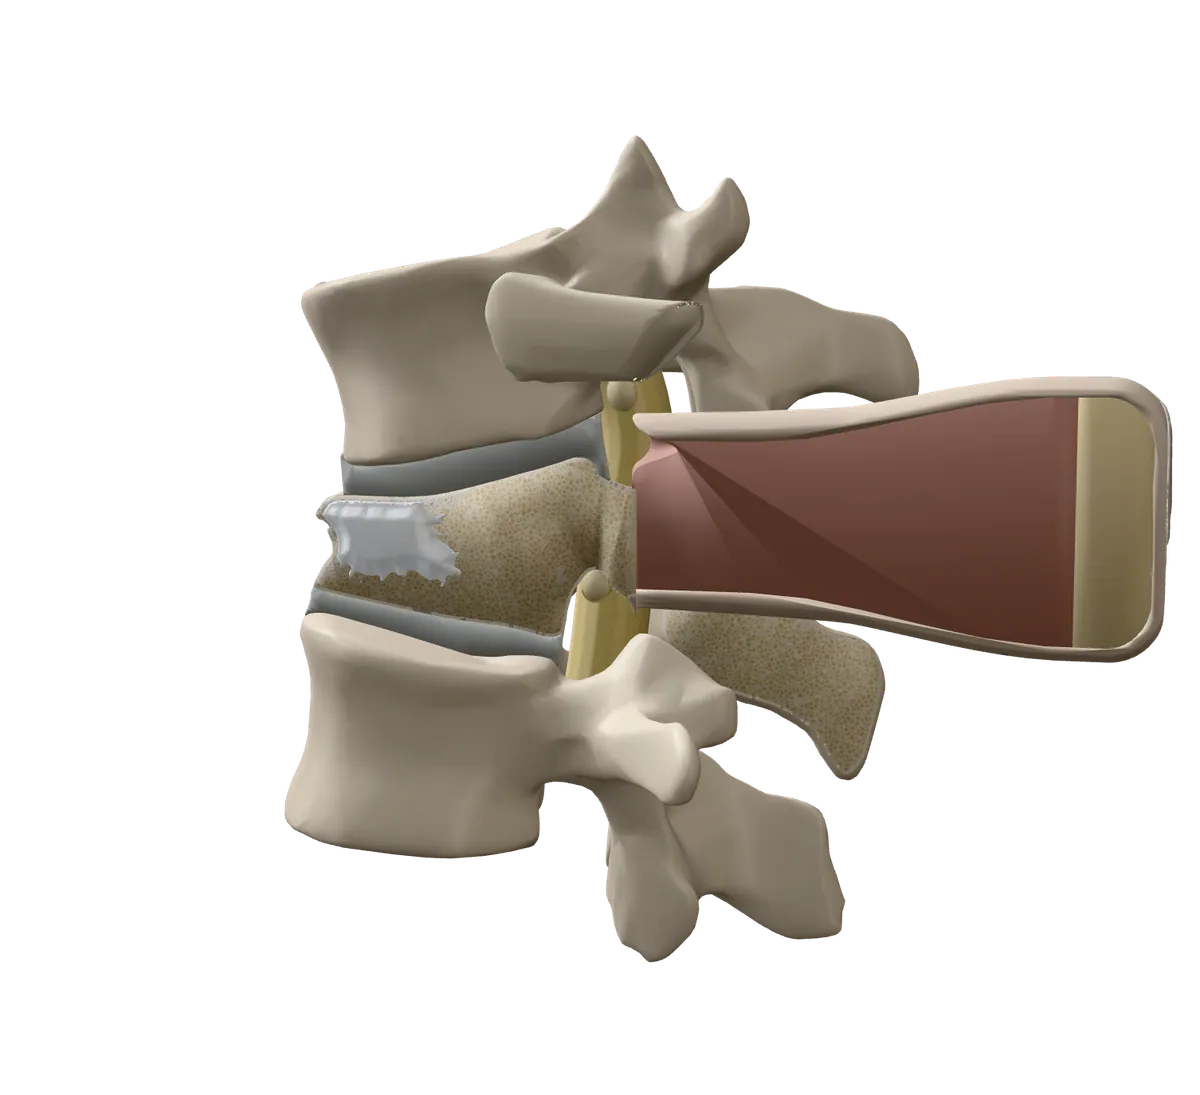
Your back may be sore where the needle went in for 2 to 3 days. Many people find their fracture pain eases right away or within about 2 days.
Good to know. You lie down and rest for 1 to 2 hours while the team checks on you. Most people can get up and walk after about an hour. Many go home the same day, and some stay overnight. Avoid heavy lifting for at least 6 weeks.
How well it works, honestly
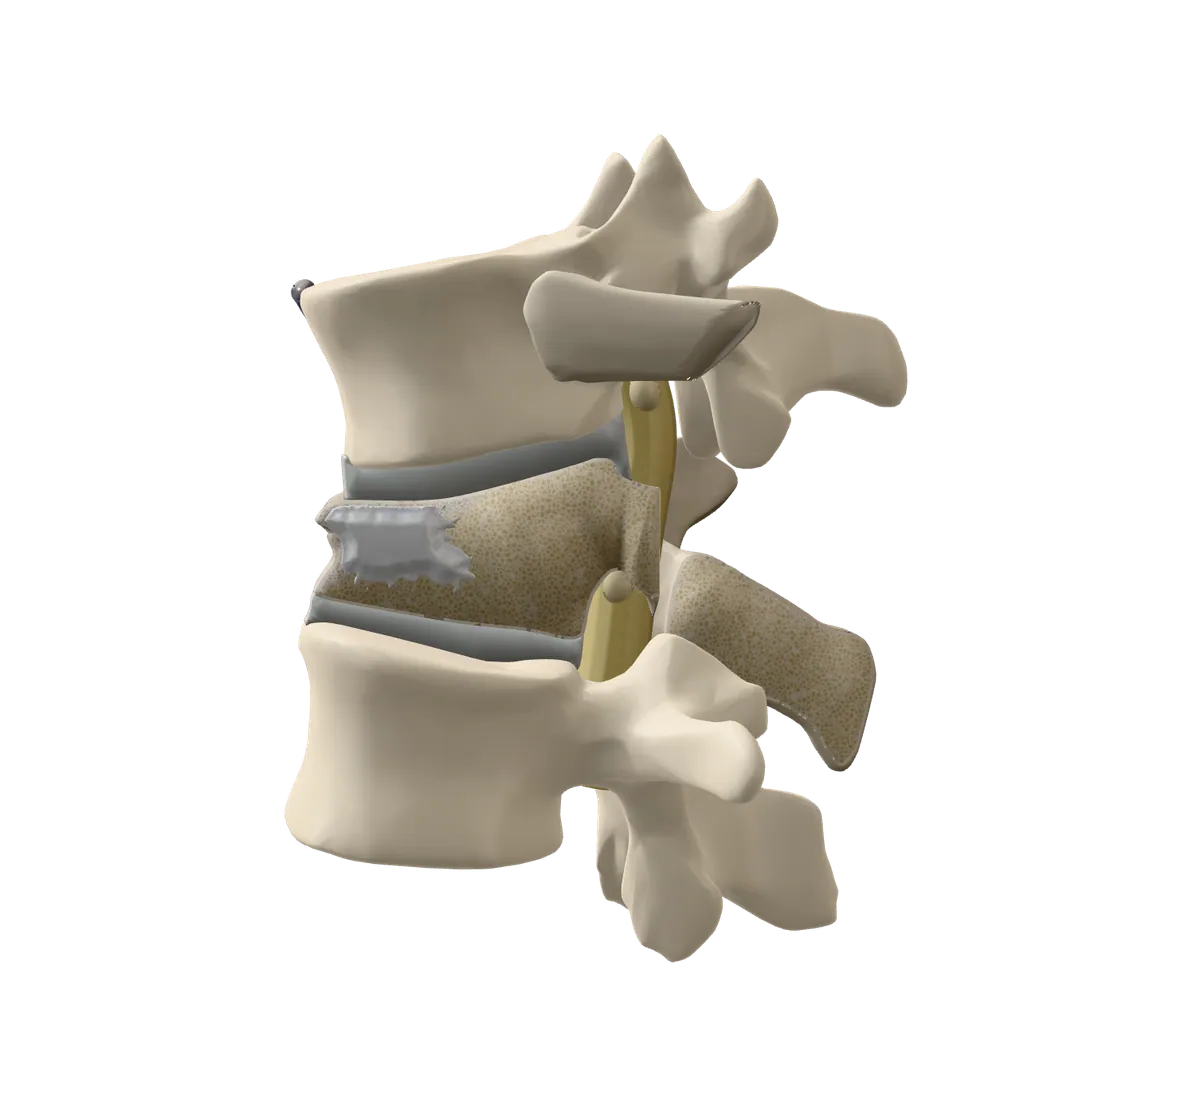
Many people feel much better. Guides from different sources say that between half and 9 in 10 people have less pain or move better afterwards.
But careful studies disagree. In some, people who had a pretend procedure improved almost as much. The treatment also does not fix weak bones.
Good to know. Getting up sooner can also help you avoid problems like pneumonia (a lung infection). Bone-strengthening medicine can lower the chance of another spine fracture by 40 to 70 percent.
Risks
Risks, explained plainly
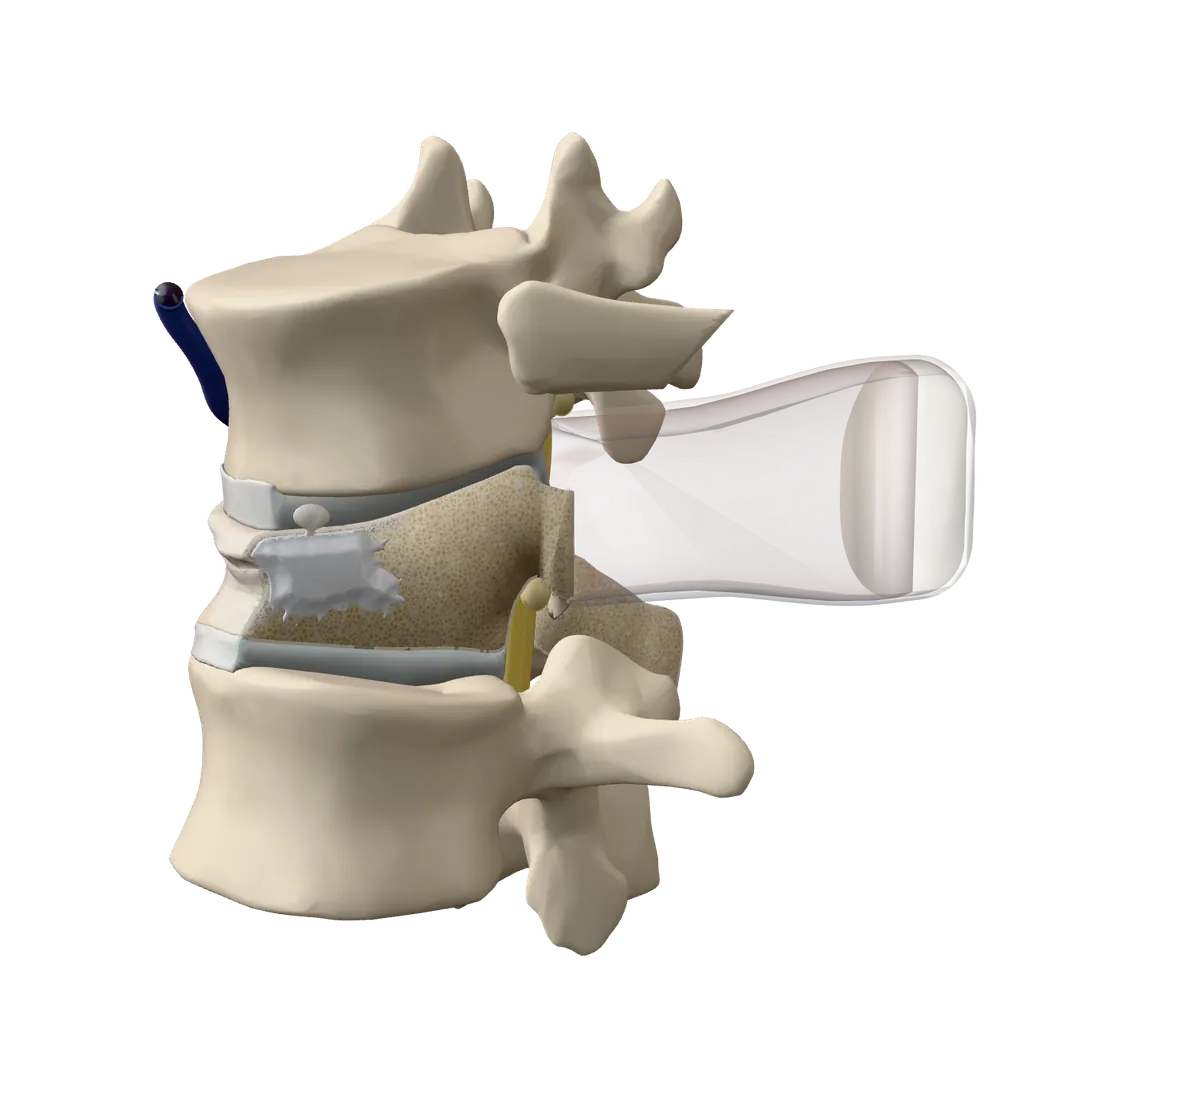
Every procedure has some risk, and most people do not have a serious problem. Each risk is listed under Benefits and risks below, with how often it happens.
The most common problem is a small cement leak that almost never causes symptoms, and serious problems are uncommon.
Your visit
Before, on the day and after. Your care team’s instructions come first if they differ.
Before your procedure
Things to do. Tick them off as you go; your ticks stay on this device only.
On the day
You change into a gown. Leave jewellery at home.
You sign a consent form once all your questions are answered.
A nurse puts a small tube (IV) in your hand or arm. Monitors check your heart rate, blood pressure and oxygen.
You may get antibiotics to prevent infection, and medicine for pain or nausea.
You lie face down on the X-ray table. Medicine through the IV makes you drowsy and relaxed. Some people have a general anesthetic instead.
Your skin is cleaned and numbed. You may feel pressure, and a tapping feeling as the needle goes into the bone. Tell the team if you feel pain.
For one bone it usually takes under an hour. More bones take longer.
Afterwards you lie down and rest for 1 to 2 hours, then you can usually get up and walk.
Recovery
- The first hours
Rest lying down for 1 to 2 hours while the team checks on you. After about an hour, most people can get up and walk. Many go home that day with an adult driver. Some stay overnight.
- Days 1 to 3
Soreness where the needle went in is normal and usually lasts 2 to 3 days. An ice pack wrapped in a cloth, for 15 minutes each hour, can help. Leave the bandage on for 48 hours and do not soak it in water. Showers are fine.
- Pain relief
Many people find their fracture pain eases right away or within about 2 days. Your usual pain medicine should be enough.
- The first weeks
Slowly do a little more each day. Avoid heavy lifting and hard exercise for at least 6 weeks. Do not drive on the day of the procedure, and ask when you can drive again.
- Follow-up
You may have a check-up visit, scans or blood tests. If you have osteoporosis, ask about treatment to protect your other bones.
When to get help
Call 9-1-1 now if you have
- Sudden trouble breathing
- Chest pain
- New weakness in your legs
- You cannot control your bladder or bowels
- Bleeding from the needle site that does not stop with firm pressure
Call the interventional radiology (IR) team today if you have
- A fever
- Swelling or a change in skin colour where the needle went in
- Back pain that is getting worse instead of better
- New numbness or tingling
Phone number added by the hospital before launch
If you can’t reach them, go to the nearest emergency department.
Not sure? Call HealthLink BC at 8-1-1
- Health questions that are not urgent, such as soreness, your bandage or your medicines, if you cannot reach the IR team
A nurse can give health advice any time, day or night.
Call 8-1-1Deaf or hard of hearing: call 7-1-1. Translation services are available in over 130 languages.
Benefits and risks
What it can do for you
- No surgical cut: just a small nick in the skin that does not need stitches.
- Usually under an hour for one bone, and often home the same day.
- Many people feel less pain right away or within a few days.
- Patient guides report that from about half to 9 in 10 people have less pain or move better afterwards. The numbers vary from study to study.
- Getting up and moving sooner can lower the risk of pneumonia (a lung infection) and help keep your muscles strong.
- Kyphoplasty may give back some of the bone’s lost height.
What can go wrong
Every procedure has some risk, and most people do not have a serious problem. Each risk is listed with how often it happens. They are grouped on one scale, from very common to very rare.
Very common: more than 1 in 10 people
A small cement leak
Scans find a small leak in about 1 in 4 to 3 in 4 treated bones. Almost all cause no symptoms.
A little cement seeps just outside the bone, often into the disc above or below. It almost never causes problems. Leaks are found less often after kyphoplasty (about 29 in 100) than after vertebroplasty (about 39 in 100).
Common: 1 in 10 to 1 in 100 people
Cement travelling to the lungs
About 2 in 100 people have cement in the lungs on scans, usually with no symptoms. Breathing problems happen to about 1 in 500 people, says one patient leaflet.
A little cement gets into a vein and travels to the lungs. Usually it causes no symptoms. In a few people, it causes breathing problems.
A new break in a nearby bone
About 1 in 10 people.
Another spine bone, often the one just above or below, breaks later. Pain can come back after a few days of relief. People with osteoporosis are at risk anyway: about 1 in 5 have another spine fracture within a year of the first. Studies disagree on whether the cement adds to this.
Uncommon: 1 in 100 to 1 in 1,000 people
Bleeding or a bruise where the needle went in
1 in 149 people had a serious bleed.
Where this number comes from
1 in 149 people had a serious bleed, in one large study.
A small bruise or a little bleeding can happen where the needle went in. A serious bleed is less common.
Cement pressing on a nerve or the spinal cord
About 1 in 500 people, says one patient leaflet. Paralysis is rarer still.
Cement, or rarely bleeding, reaches the tunnel behind the bone and presses on a nerve or the spinal cord. This can cause pain, numbness or weakness, and may need an urgent operation.
Rare: 1 in 1,000 to 1 in 10,000 people
Infection
Fewer than 1 in 1,000 people need antibiotics for an infection.
Germs get into the treated bone. Antibiotics are often given beforehand to prevent this.
Other options
Questions to ask
Tick the ones you want to ask. Your ticks stay on this device only.
Check your understanding
Nothing is saved. It is just for you.
Both fill the broken bone with cement through a needle. Kyphoplasty adds a balloon step first.
Medical bone cement goes in as a thick paste and sets hard within about 20 minutes, like a cast on the inside.
It treats the one broken bone. Bone-strengthening medicine is what lowers the chance of new fractures.
Sudden trouble breathing, chest pain, or new weakness in your legs needs emergency help right away.
Words used
- Vertebra
- One of the bones that stack up to make your spine. More than one are called vertebrae.
- Vertebral body
- The thick, round front part of a vertebra that carries your weight.
- Compression fracture
- A break where a vertebra squashes down and loses height.
- Osteoporosis
- A condition where bones become thin and weak, so they break more easily.
- Vertebroplasty
- Filling a broken vertebra with bone cement through a needle.
- Kyphoplasty
- Like vertebroplasty, but a small balloon first makes space in the bone.
- Bone cement
- A medical paste, like toothpaste, that sets hard inside the bone. Its full name is PMMA.
- Trocar
- A hollow needle the doctor guides into the bone.
- Pedicle
- A short, strong bridge of bone at the back of a vertebra. The needle usually passes through it.
- Fluoroscopy
- Live X-ray video that lets the doctor watch the needle and the cement.
- Sedation
- Medicine that makes you drowsy and relaxed, but not fully asleep.
- Interventional radiologist
- A doctor who treats problems through tiny openings, guided by imaging.
Sources
- RadiologyInfo.org (RSNA and ACR). Vertebroplasty and kyphoplasty (reviewed June 2026)
- Cardiovascular and Interventional Radiological Society of Europe (CIRSE). Vertebral augmentation, patient information
- Society of Interventional Radiology. Back pain, patient information
- Cleveland Clinic. Kyphoplasty
- Cleveland Clinic. Compression fractures
- NHS (UK), hospital trust patient leaflet. Vertebroplasty (repair of vertebrae with bone cement), May 2026
- NHS (UK), health board patient booklet. A guide to your vertebroplasty (2024)
- National Institute for Health and Care Excellence (NICE). TA279: Percutaneous vertebroplasty and percutaneous balloon kyphoplasty for treating osteoporotic vertebral compression fractures
- Osteoporosis Canada. Facts and stats
- Cochrane Database of Systematic Reviews. Percutaneous vertebroplasty for osteoporotic vertebral compression fracture (2018)
- BMJ. Vertebroplasty versus sham procedure for painful acute osteoporotic vertebral compression fractures (VERTOS IV), 2018
- The Lancet. Safety and efficacy of vertebroplasty for acute painful osteoporotic fractures (VAPOUR), 2016
- The Lancet. Efficacy and safety of balloon kyphoplasty compared with non-surgical care for vertebral compression fracture (FREE), 2009
- Journal of Bone and Mineral Research (ASBMR). The efficacy and safety of vertebral augmentation: a second ASBMR task force report (2019)
- Revista da Associação Médica Brasileira. Kyphoplasty versus vertebroplasty for osteoporotic vertebral compression fractures: a systematic review and meta-analysis of randomized trials (2026)
- European Spine Journal. Clinical significance of cement leakage in kyphoplasty and vertebroplasty: a systematic review (2024)
- International Journal of Surgery. Risk factors for pulmonary cement embolism associated with percutaneous vertebral augmentation: a systematic review and meta-analysis (2022)
- Medicine (Baltimore). Complications of percutaneous vertebroplasty: an analysis of 1100 procedures performed in 616 patients (2016)
- Surgery Research and Practice. Percutaneous vertebral body augmentation: an updated review (2014)
- Frontiers in Surgery. Incidence of new osteoporotic adjacent vertebral body fractures: conservative treatment compared with vertebral body augmentation, a systematic review and meta-analysis (2025)
- Medicina (Kaunas). Complications of percutaneous vertebroplasty: a pictorial review (2023)
- American Academy of Orthopaedic Surgeons (OrthoInfo). Osteoporosis and spinal fractures
- Osteoporosis Canada. Osteoporosis and pain: helping your body help itself (April 2021)
- Canadian Anesthesiologists Society. Guidelines to the practice of anesthesia, revised edition 2026, section 4.2 (fasting)
- HealthLink BC. HealthLink BC 8-1-1 services
About this guide
- Status
- Draft: not yet reviewed by the clinical team. The interventional radiology team will review it before it is used with patients, and the date of that review will show here.
- How it was written
- Drafted with AI writing tools from 24 published sources, then fact-checked against those sources by a separate AI check. Anything the sources did not support was taken out. The interventional radiology team will review it before it is used with patients.
- Last edited
- 14 October 2026
- Document
- Pathway P-003 · Version 0.5 · Last reviewed: not yet · Next review: 12 months after sign-off · Owner: the interventional radiology team
Was this guide clear?
Tell us if anything was hard to follow, or if something on the page looks wrong. Please do not include details about your own health. For questions about your care, contact your care team.
Both open an email to the project team. Project email: added before launch