Uterine fibroid embolization
Also called UFE
DraftNot yet reviewed by the clinical team · Last edited 14 October 2026
Fibroids are common growths in the uterus that can cause heavy periods, pain and pressure. UFE shrinks them by cutting off their blood supply through a small opening at the groin or wrist. There is no surgery, and your uterus stays in place.
- Awake or drowsy
- with medicine to help you relax and control pain
- A small opening
- at the groin or wrist, no stitches
- Home that day or the next
- depending on the hospital
- 1 to 2 weeks
- to get back to normal, for most people
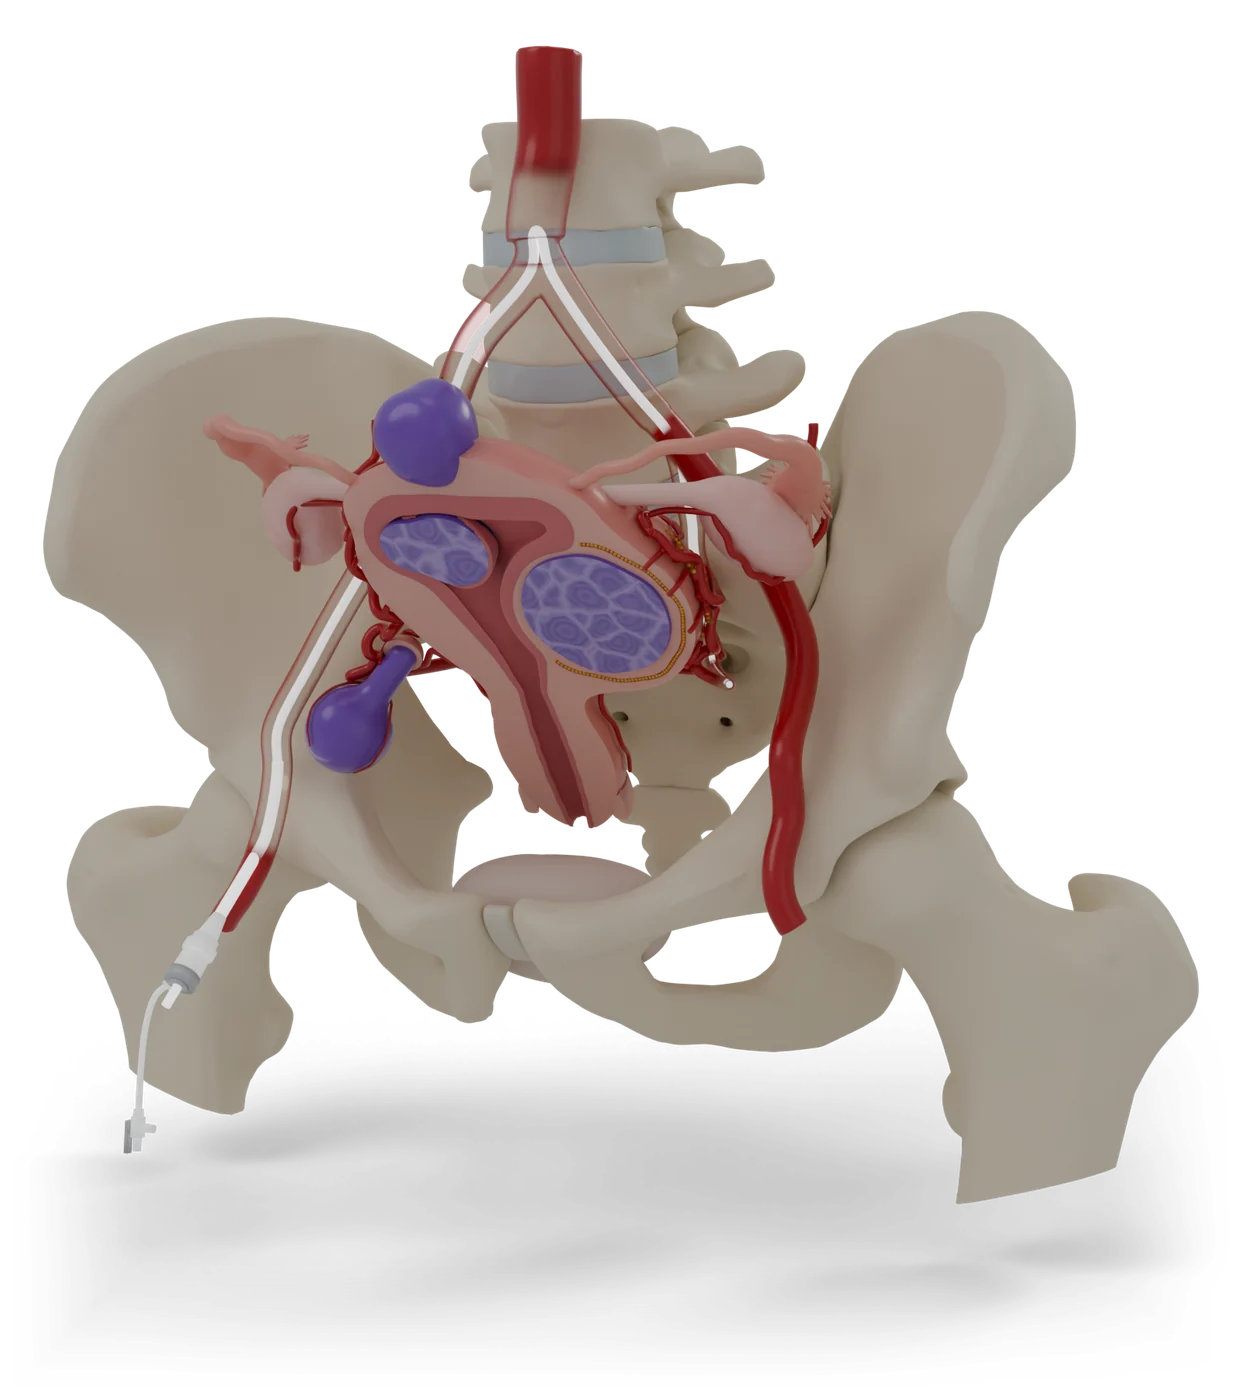
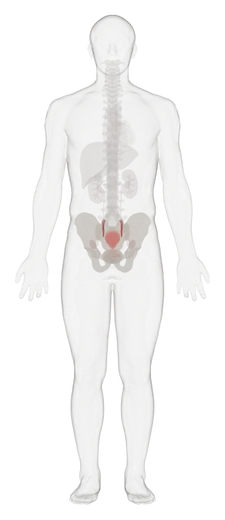
Where this happens: Pelvis. UFE treats the uterus, low in the belly between the hip bones. The thin tube goes in at the groin or the wrist.
The short version
Fibroids are growths in the wall of the uterus that are not cancer, and they can cause heavy periods, pain and pressure.
In UFE, a doctor slides a thin tube in through a small opening at your groin or wrist and steers it to your uterus, watching on an X-ray screen.
Tiny particles go through the tube and block the small blood vessels that feed the fibroids, so they shrink over the following months while your uterus stays in place.
Cramps can be strong for the first few days. Most people are back to normal in 1 to 2 weeks, and about 8 or 9 in 10 feel much better.
Step through it on the model
Start from the beginningEach step shows one thing on a 3D model you can turn. Jump to any step.
See all 12 steps
What it treats
Your visit
What to do before, what happens on the day, and what recovery is usually like. Your care team will give you instructions for your own situation. Follow theirs if they differ.
Before your procedure
Things to do. Tick them off as you go; your ticks stay on this device only.
On the day
Getting ready. You change into a gown. A nurse checks your blood pressure and heart rate and places an IV in your arm.
Bladder tube. Many hospitals place a soft tube (catheter) in your bladder to keep you comfortable during and after.
Pain control. Pain medicine is given before, during and after. Many hospitals use a pump you press yourself. It is set so you cannot take too much.
Sedation. Medicine through the IV helps you relax. You may stay awake or doze. Most people do not need a general anesthetic.
Numbing. The skin at your groin or wrist is numbed. It may sting or burn for a moment.
The X-ray dye. You may feel warm in your pelvis, or feel like you wet yourself, for a few seconds. This is normal.
How long. Often about an hour in the procedure room. It can be from 30 minutes to about 3 hours. Expect to be in the department for longer.
Right after. If the groin was used, you lie flat and keep your leg still for a few hours, often about 4.
Going home. Some people go home the same day. Others stay one night. You go home when you can eat, drink, walk, use the toilet and manage pain with pills.
Recovery
- The first day
You rest in recovery while the team gives you medicine for pain and nausea. Cramps are usually worst in the first 24 hours.
- Days 1 to 7
Most people have cramps (sometimes strong), a low fever, nausea and tiredness. This is expected, and medicine helps. It is called post-embolization syndrome. It usually settles in 2 to 7 days. For some it lasts a couple of weeks. Take the medicine you were sent home with.
- Weeks 1 to 2
Many people can do light activity after a few days. Most are back to normal in 1 to 2 weeks. Ask when you can drive, work, exercise and have sex.
- Discharge
Discharge from the vagina can last up to 2 weeks, or come and go for a few months. It comes from the fibroids breaking down.
- Your next periods
Bleeding is often lighter from the first period. You may skip a period or two.
- About 4 to 6 weeks
You will likely have a follow-up visit with the IR or gynaecology team.
- 3 to 9 months
Fibroids keep shrinking, and the full effect shows by about 6 months. You may have another MRI or ultrasound to check.
- If you could get pregnant
Ask how long to wait before trying. Some sources advise using birth control for 6 months.
When to get help
Call 9-1-1 now if you have
- Trouble breathing.
- Chest pain.
- Bleeding at the groin or wrist that does not stop with firm pressure.
- A lump at the groin or wrist that grows fast.
- Fainting.
- Feeling very unwell with a fever, a racing heart or confusion.
- Sudden weakness or numbness.
- A drooping face.
- Trouble speaking.
Call the interventional radiology (IR) team today if you have
- A fever after the first 3 days, or a fever with chills.
- Discharge that smells bad, especially with a fever.
- Severe pain in your belly or pelvis.
- More pain where the tube went in.
- Heavier bleeding from the vagina.
- Passing pieces of tissue.
- Redness, swelling or fluid coming from where the tube went in.
- A painful, swollen leg.
Phone number added by the hospital before launch
If you can’t reach them, go to the nearest emergency department.
Not sure? Call HealthLink BC at 8-1-1
- Questions about your medicines or their side effects.
- You are not sure if a symptom is normal, and it is not an emergency.
A nurse can give health advice any time, day or night.
Call 8-1-1Deaf or hard of hearing: call 7-1-1. Translation services are available in over 130 languages.
Benefits and risks
What it can do for you
- Your uterus stays in place.
- No surgical cut and no stitches. The opening is smaller than a quarter of an inch.
- Most people do not need a general anesthetic.
- All your fibroids are treated in one go, even small ones.
- A shorter hospital stay and a faster return to daily life than surgery. Most people are back to normal in 1 to 2 weeks, compared with about 6 weeks after a hysterectomy.
- On average, fibroids shrink to about half their volume.
- About 8 or 9 in 10 people say their symptoms get much better.
What can go wrong
Every procedure has some risk, and most people do not have a serious problem. Each risk is listed with how often it happens. They are grouped on one scale, from very common to very rare.
Very common: more than 1 in 10 people
Needing more treatment later
About 15 to 32 in 100 people within 2 years.
Where this number comes from
About 15 to 32 in 100 people within 2 years, in one large review. In one trial, 24 in 100 by 4 years.
Sometimes symptoms do not improve enough, or new fibroids grow. Then you may need another procedure or surgery. This is more likely than after surgery. In one large review, about 7 in 100 needed more treatment within 2 years after surgery. In one trial, 13 in 100 needed more treatment by 4 years after myomectomy.
Common: 1 in 10 to 1 in 100 people
Cramps, fever and nausea afterwards
About 3 in 100 people had it bad enough to be counted as a complication.
Where this number comes from
In trials, about 3 in 100 people had it bad enough to be counted as a complication.
Cramps, a low fever, nausea and tiredness for a few days are expected after UFE, as the fibroids lose their blood supply and break down. They are part of normal recovery, and medicine helps. This is called post-embolization syndrome. In a few people it is bad enough to be counted as a complication.
A fibroid passing out
About 2 to 5 in 100.
Where this number comes from
About 2 to 5 in 100. Single studies range from 1 to 10 in 100.
A fibroid, or part of one, can come loose and pass out through the vagina. This can cause cramps, bleeding or discharge. Sometimes a small procedure is needed to remove it. It can happen weeks, months or even years later. If you pass pieces of tissue, call the IR team the same day.
Periods stopping early
About 1 to 5 in 100. Periods stop for good in fewer than 2 in 100.
If particles reach the blood supply of the ovaries, periods may stop early (early menopause). This can happen because the arteries of the ovaries link up with the uterine arteries. It is more likely if you are over 45 (one source says over 40).
Infection of the uterus
About 1 to 2.5 in 100.
Where this number comes from
About 1 to 2.5 in 100, depending on the study.
The treated fibroid or the uterus can get infected. Signs are severe pain, a high fever and bad-smelling discharge. Most infections are treated with antibiotics. Very rarely, the uterus has to be removed (hysterectomy). In a very small number of cases a severe infection can be life threatening. That is why a fever with bad-smelling discharge needs a call the same day.
Uncommon: 1 in 100 to 1 in 1,000 people
Problems where the tube went in
Fewer than 1 in 100 people have a problem at the entry point, with an experienced doctor. How often stroke happens is not known.
You may get a bruise or a small lump where the tube went in. Rarely, the artery there is damaged or the opening gets infected. With the wrist route, there is also a very small risk of stroke. A stroke is when blood flow to part of the brain is blocked.
Blood clots in the legs or lungs
Fewer than 1 in 100.
Where this number comes from
Fewer than 1 in 100. One series had 1 in 200.
A clot can form in a leg vein and travel to the lungs. Signs are a painful, swollen leg, chest pain or trouble breathing.
Reaction to the X-ray dye
About 6 in 1,000 people have an allergy-type reaction to this kind of dye. Serious reactions are rare, about 4 in 10,000.
Some people react to the dye. Most reactions are mild, like itching. Rarely, a reaction affects breathing or blood pressure. Tell the team about any past reaction.
Rare: 1 in 1,000 to 1 in 10,000 people
Particles going to the wrong place
It has only been reported in single cases, so no source gives a reliable number.
Particles can reach an artery that feeds something else, like the bladder, bowel, buttock or the skin between the legs. This can cause pain or damage there. The team checks with X-ray dye before releasing particles to prevent this.
If you want to become pregnant
The effect of UFE on getting pregnant is not fully known. Healthy pregnancies after UFE have been reported, but UFE is not usually the first choice if you hope to get pregnant. Your doctor may suggest surgery to remove the fibroids (myomectomy) instead, or advice from a fertility specialist first. Raise your plans early so they are part of the decision.
Other options
Other options (6)
Questions to ask
Tick the ones you want to ask. Your ticks stay on this device only.
Check your understanding
Check your understanding (5)
Nothing is saved. It is just for you.
Tiny particles block the fibroids’ blood supply, so they shrink and soften. Nothing is cut out, and the uterus stays.
A small opening at the groin or wrist. The skin is numbed first, and no stitches are needed.
This is post-embolization syndrome. It is expected and usually settles in 2 to 7 days. Bad-smelling discharge with a fever is not normal: call the IR team the same day.
On average fibroids shrink to about half their volume (the space they take up). Symptoms often get much better even though the fibroids are still there.
Many fibroids need no treatment. Other good options include medicines and surgery. Your team will help you choose.
Words used
Words used (12)
- Fibroid
- A growth of muscle and tough tissue in the wall of the uterus. Not cancer. Also called a leiomyoma.
- Uterus
- The womb. The muscle organ where periods come from and where a baby grows.
- Uterine artery
- One of two arteries, one on each side, that carry blood to the uterus.
- Embolization
- Blocking a blood vessel on purpose, here with tiny particles.
- Interventional radiologist
- A doctor who treats problems through tiny openings, guided by X-ray or other images.
- Catheter
- A thin, bendy tube.
- Fluoroscopy
- Live X-ray video used to guide the catheter.
- Contrast (dye)
- A liquid that shows up on X-ray, so the arteries can be seen.
- Sedation
- Medicine that makes you relaxed and sleepy. You may stay awake.
- Post-embolization syndrome
- Cramps, low fever, nausea and tiredness for a few days after UFE. Expected.
- Myomectomy
- Surgery to remove fibroids and keep the uterus.
- Hysterectomy
- Surgery to remove the uterus.
Sources
Sources (19)
- Society of Interventional Radiology (SIR). Uterine fibroids, patient page (reviewed September 2024)
- RadiologyInfo.org (ACR and RSNA). Uterine fibroid treatment (reviewed October 2024)
- Cardiovascular and Interventional Radiological Society of Europe (CIRSE). Uterine artery embolization, patient information leaflet (2025)
- CIRSE. Embolisation for uterine fibroids, patient page
- CIRSE (Cardiovascular and Interventional Radiology, 2015). Standards of practice: uterine artery embolization for symptomatic leiomyomata
- British Society of Interventional Radiology (BSIR). Uterine artery embolisation, patient information leaflet
- HealthLink BC. Uterine fibroid embolization (UFE), treatment overview
- NHS. Fibroids
- NHS. Fibroids: treatment
- Canadian Association for Interventional Radiology (CAIR). Uterine fibroid tumours: symptoms and treatment
- Society of Obstetricians and Gynaecologists of Canada (SOGC). Guideline No. 461: The management of uterine fibroids (2025), key messages
- Cochrane. Uterine artery embolization for symptomatic uterine fibroids (2014)
- European Journal of Obstetrics and Gynecology and Reproductive Biology: X (2022). Uterine artery embolization or myomectomy: four-year follow-up of a randomised trial (FEMME)
- Seminars in Interventional Radiology (2006). Complications of uterine fibroid embolization
- ISRN Obstetrics and Gynecology (2011). Uterine artery embolization as nonsurgical treatment of uterine myomas
- American Family Physician (2000). Uterine fibroid embolization
- Radiopaedia. Iodinated contrast media adverse reactions
- HealthLink BC. HealthLink BC home page (8-1-1 service hours)
- HealthLink BC. HealthLink BC 8-1-1 services
About this guide
About this guide
- Status
- Draft: not yet reviewed by the clinical team. The interventional radiology team will review it before it is used with patients, and the date of that review will show here.
- How it was written
- Drafted with AI writing tools from 18 published sources, then fact-checked against those sources by a separate AI check. Anything the sources did not support was taken out. The interventional radiology team will review it before it is used with patients.
- Last edited
- 14 October 2026
- Document
- Pathway P-001 · Version 0.5 · Last reviewed: not yet · Next review: 12 months after sign-off · Owner: the interventional radiology team
Was this guide clear?
Tell us if anything was hard to follow, or if something on the page looks wrong. Please do not include details about your own health. For questions about your care, contact your care team.
Both open an email to the project team. Project email: added before launch