DraftNot yet reviewed by the clinical team · Last edited 14 October 2026
Prostate artery embolization
PAE eases the symptoms of an enlarged prostate by slowing its blood supply, so it shrinks. It is done through a tiny opening at the groin or wrist while you are awake, with no surgical cut.
The short version
- As men get older, the prostate often grows and squeezes the tube that carries pee, which can make peeing hard.
- In PAE, a doctor puts a thin tube into an artery at the groin or wrist and guides it to the small arteries that feed the prostate.
- Tiny beads go through the tube to slow the blood flow, so over the next weeks the prostate shrinks.
- Most men go home the same day, and peeing often gets easier within 4 to 6 weeks.
What it treats
The prostate sits just under the bladder
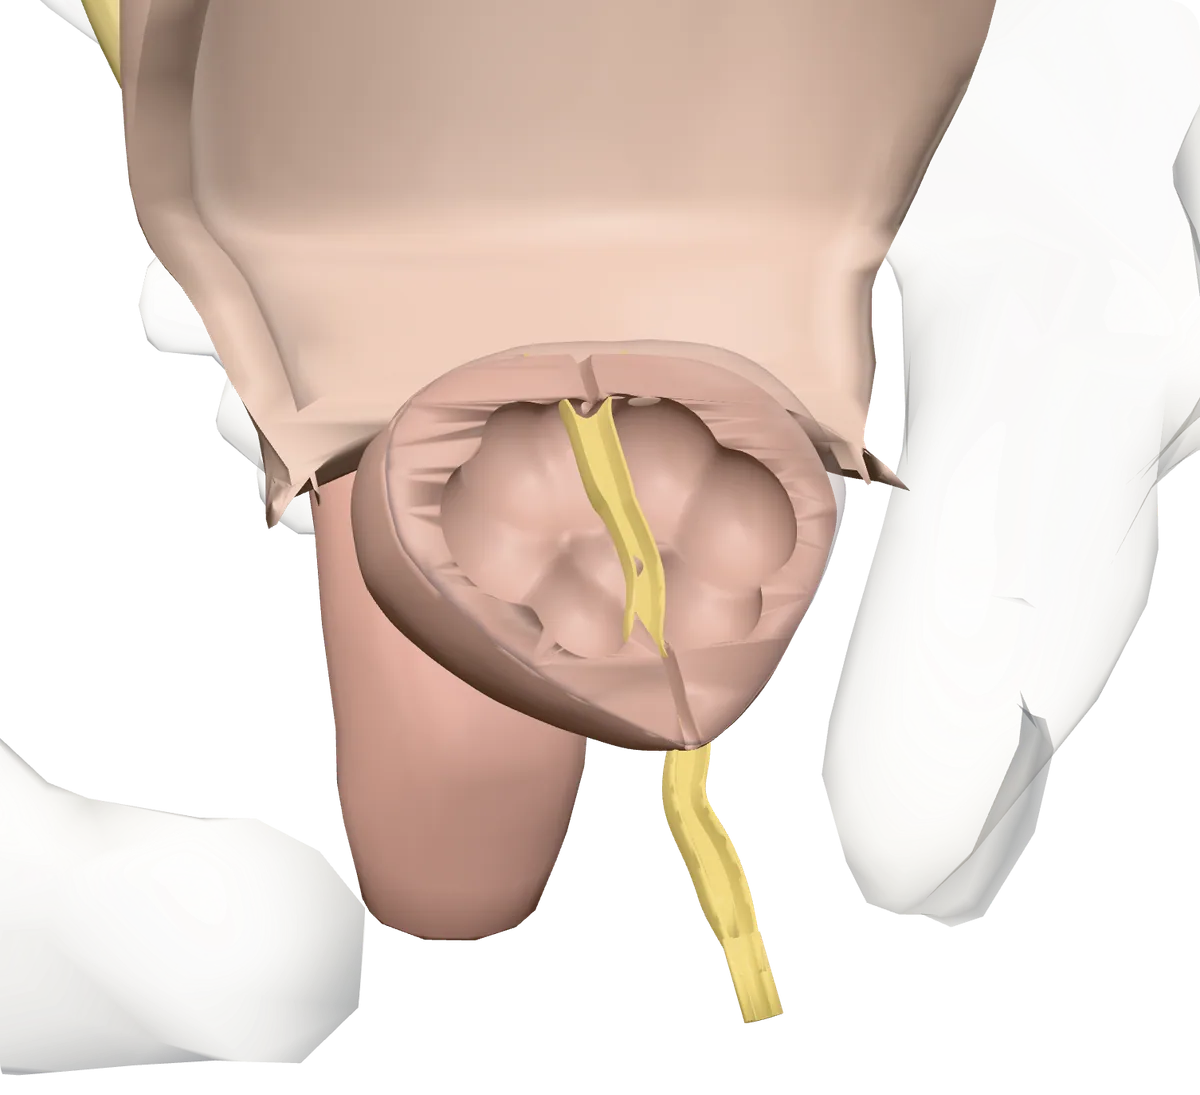
The prostate is a small gland. It sits just below the bladder and in front of the rectum. In younger men, it is about the size of a walnut.
The urethra is the tube that carries pee out of the body. It runs right through the middle of the prostate.
Good to know. The prostate also makes some of the fluid in semen.
With age, the prostate often grows
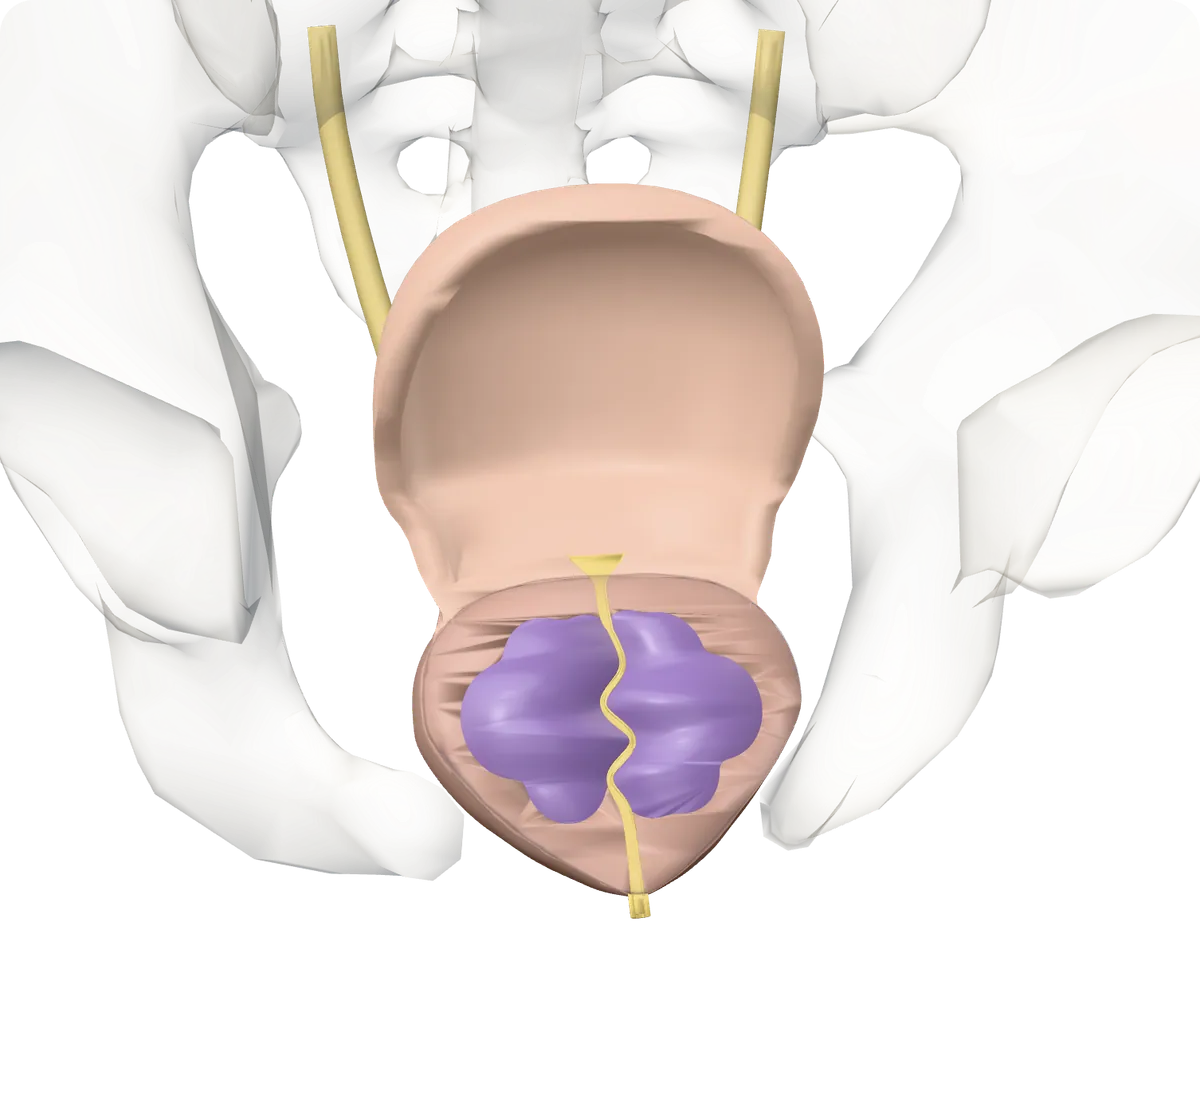
An enlarged prostate is very common as men get older. It is not cancer. Doctors call it benign prostatic hyperplasia, or BPH.
As the prostate grows, it can squeeze the urethra. That can mean a weak stream, peeing often, getting up at night to pee, or feeling that your bladder is never quite empty.
Good to know. By age 80, as many as 8 in 10 men have an enlarged prostate.
How PAE helps
Small arteries feed the prostate
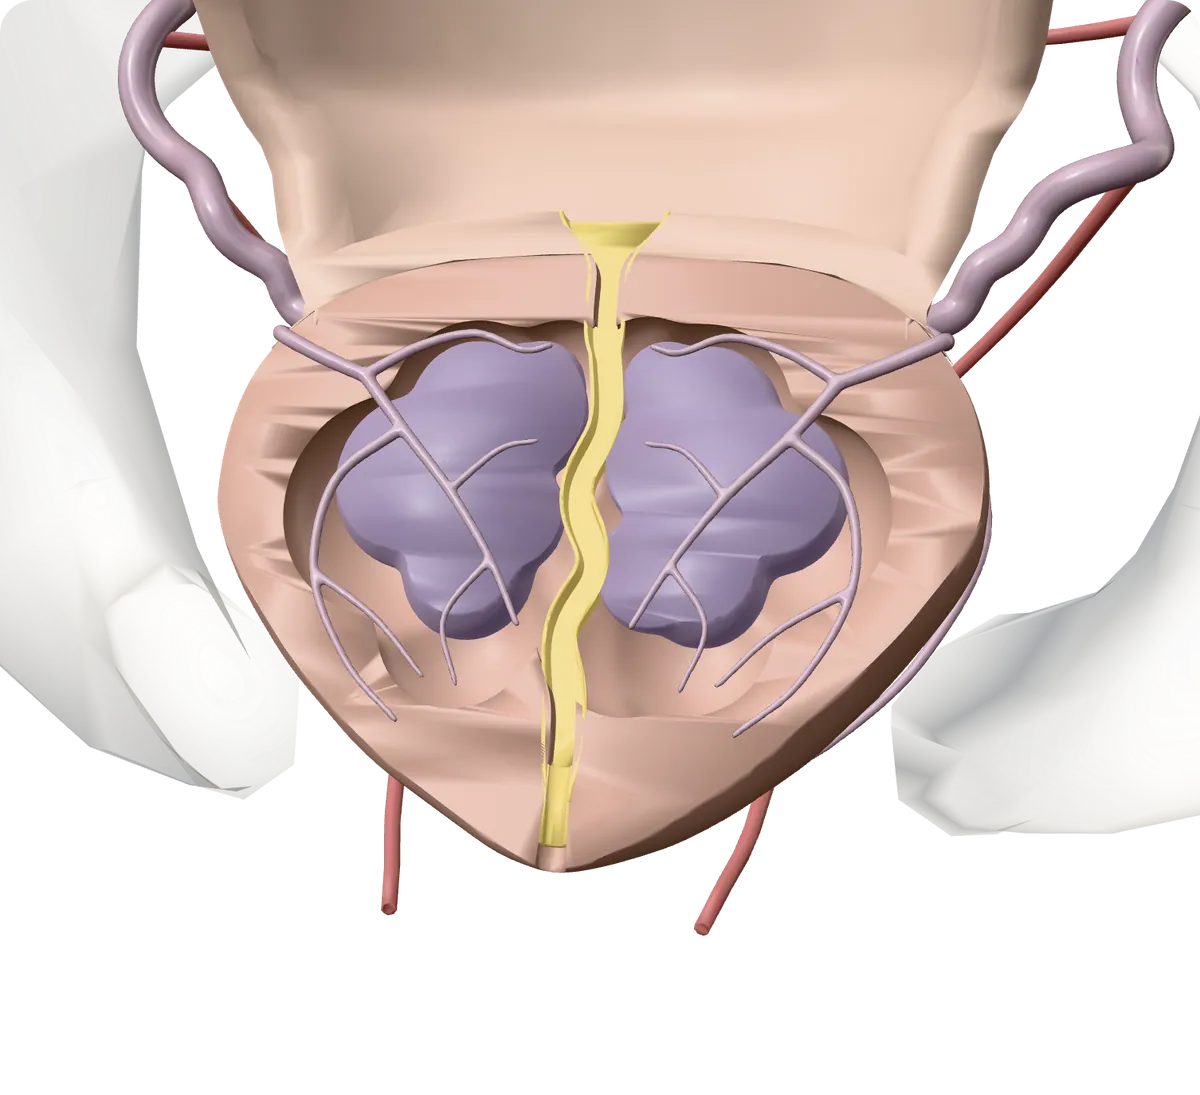
Blood reaches the prostate through small arteries on the left and right sides. They branch off larger arteries deep in the pelvis.
PAE blocks these small arteries. With less blood, the treated part of the prostate shrinks. That eases the squeeze on the urethra.
Who PAE can help
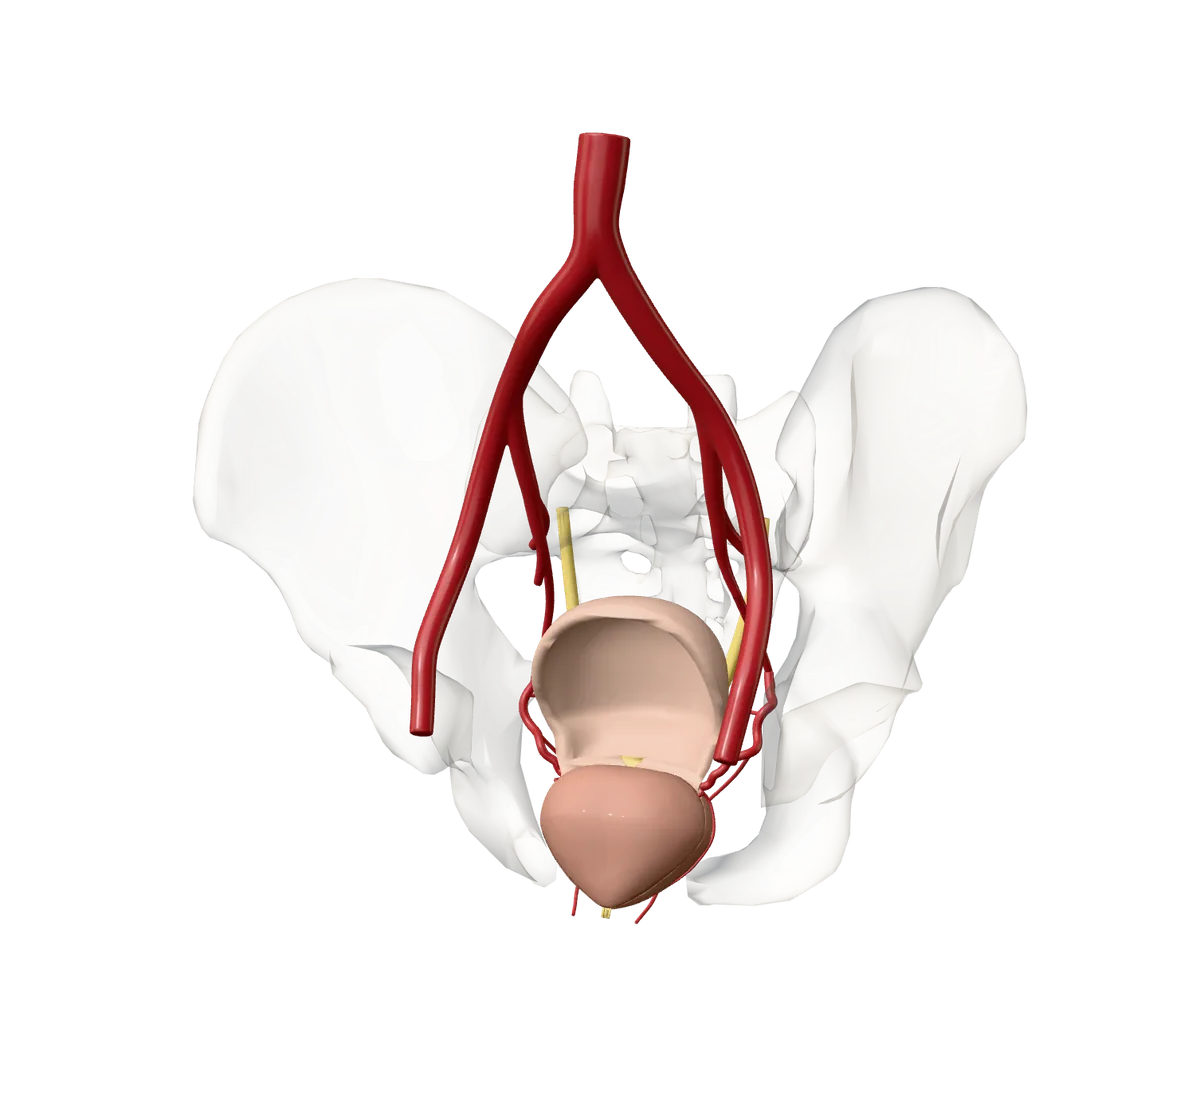
PAE is for men whose symptoms bother them, especially when pills have not helped or cause side effects. It can also suit men who do not want surgery, cannot stop blood thinners, have a very large prostate, or need a catheter to pee.
PAE is done by an interventional radiologist (IR doctor). This doctor treats problems through tiny openings, guided by imaging such as X-rays.
Good to know. You will usually see a urologist too. Together, you decide if PAE is right for you.
Getting ready
Before the day: a map of your arteries
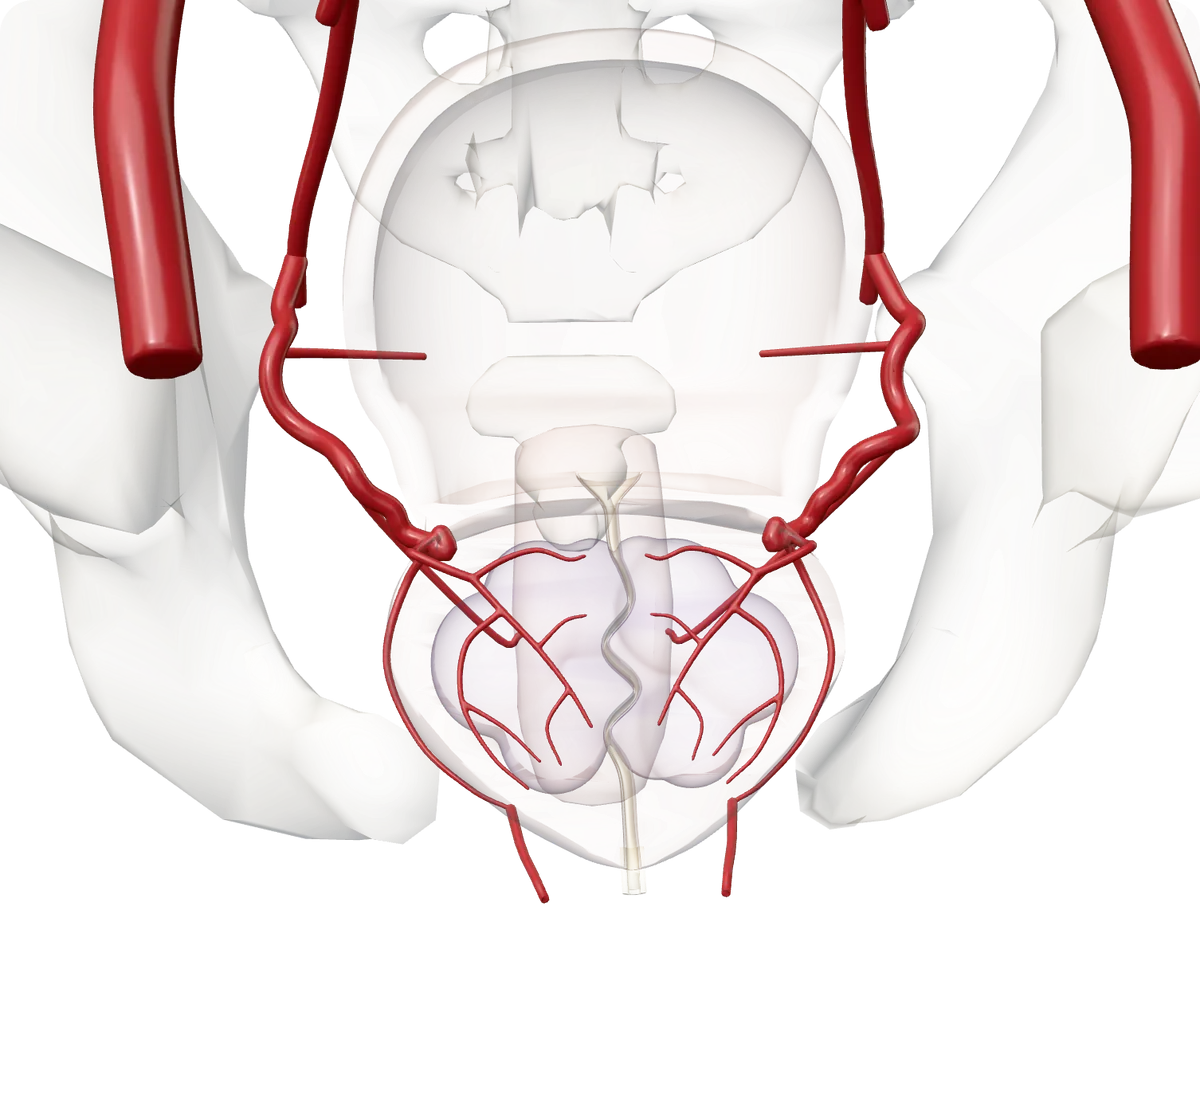
The team needs a map of your arteries, often from a CT scan with dye. These arteries are small and differ from person to person, so the map helps plan the route.
Good to know. You may also have blood tests, including a PSA test. Tell the team about all your medicines, especially blood thinners. You usually stop eating 6 hours before. Plan for an adult to take you home and stay with you that night.
The procedure
A tiny opening at the groin or wrist
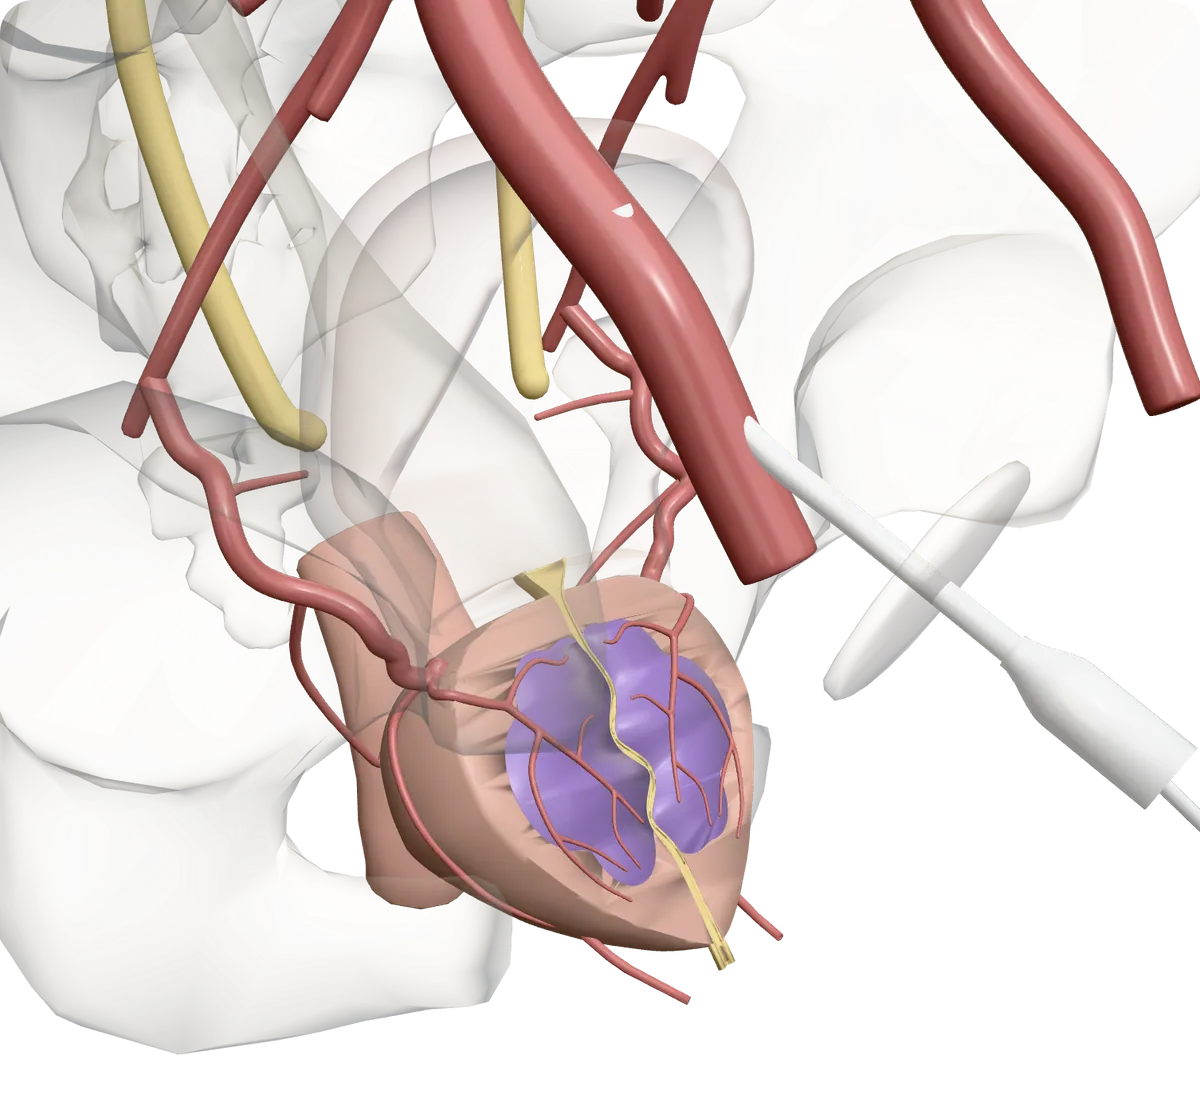
You stay awake. You can also have medicine to help you relax. The skin at the top of your leg (the groin) or at your wrist is numbed.
The doctor puts a needle into the artery there and slides in a short, thin tube. Ultrasound helps find the artery. There is no surgical cut.
A thin tube travels to the prostate arteries
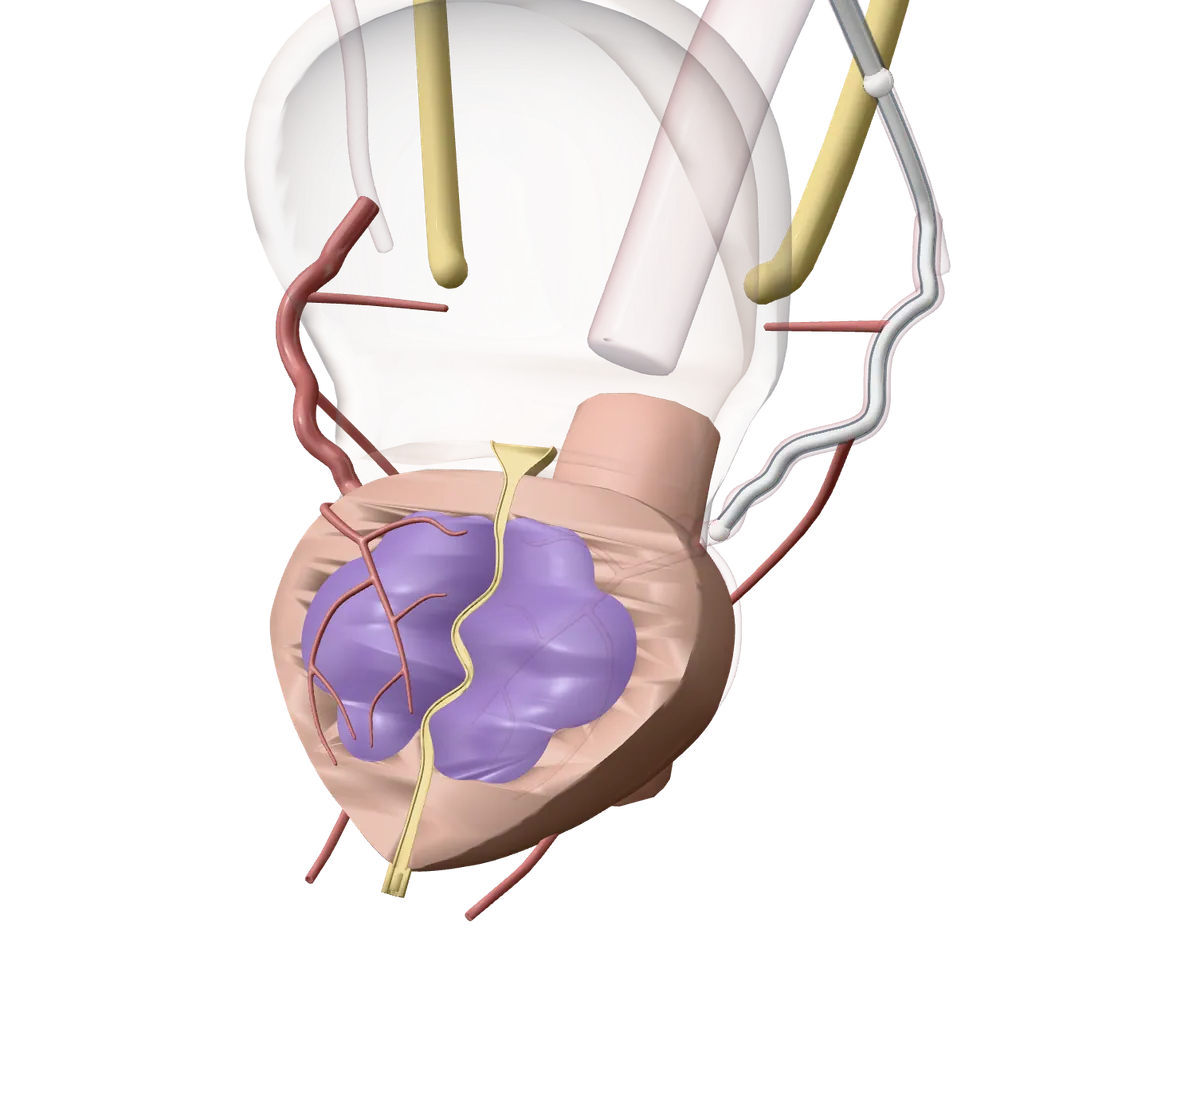
A catheter is a thin, flexible tube. It goes up the artery and into the pelvis while the doctor watches on an X-ray screen.
Dye makes the arteries show up. Then an even thinner tube, called a microcatheter, goes into the small prostate artery itself.
Good to know. Most men feel little or no pain during this. The X-ray machine may turn around you to make a 3D picture. The X-ray dose is about the same as 2 to 3 CT scans of the belly.
Tiny beads slow the blood flow
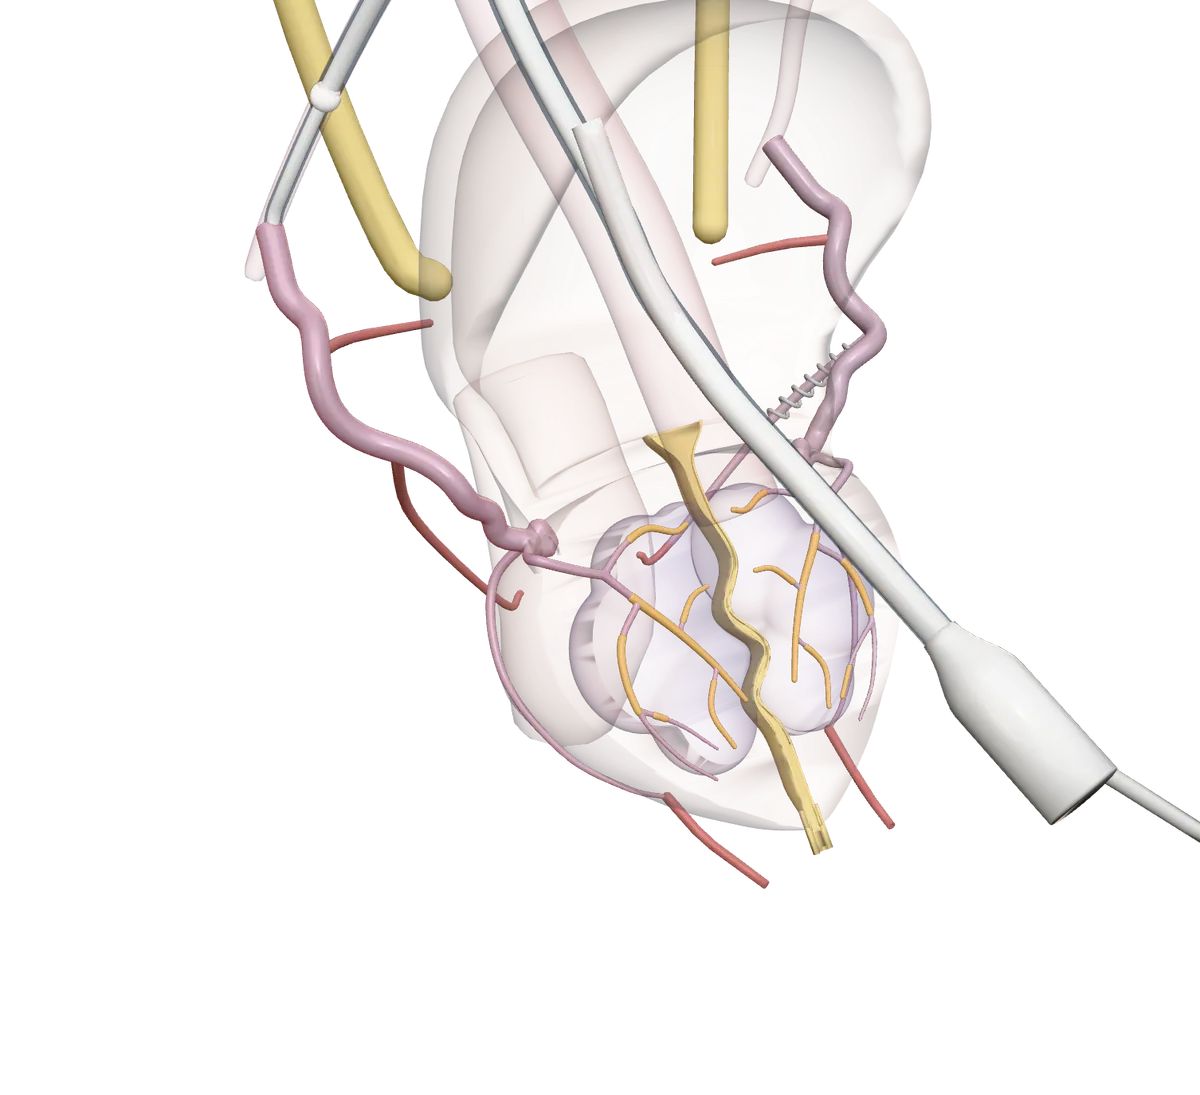
Through the tube, the doctor puts in tiny beads, smaller than grains of sand. They lodge in the small vessels inside the prostate and slow the blood flow there.
If a small artery links to the bladder, rectum or penis, the doctor may first close it with a tiny metal coil. Then the same steps are done on the other side, often through the same opening.
The tube comes out, and you rest
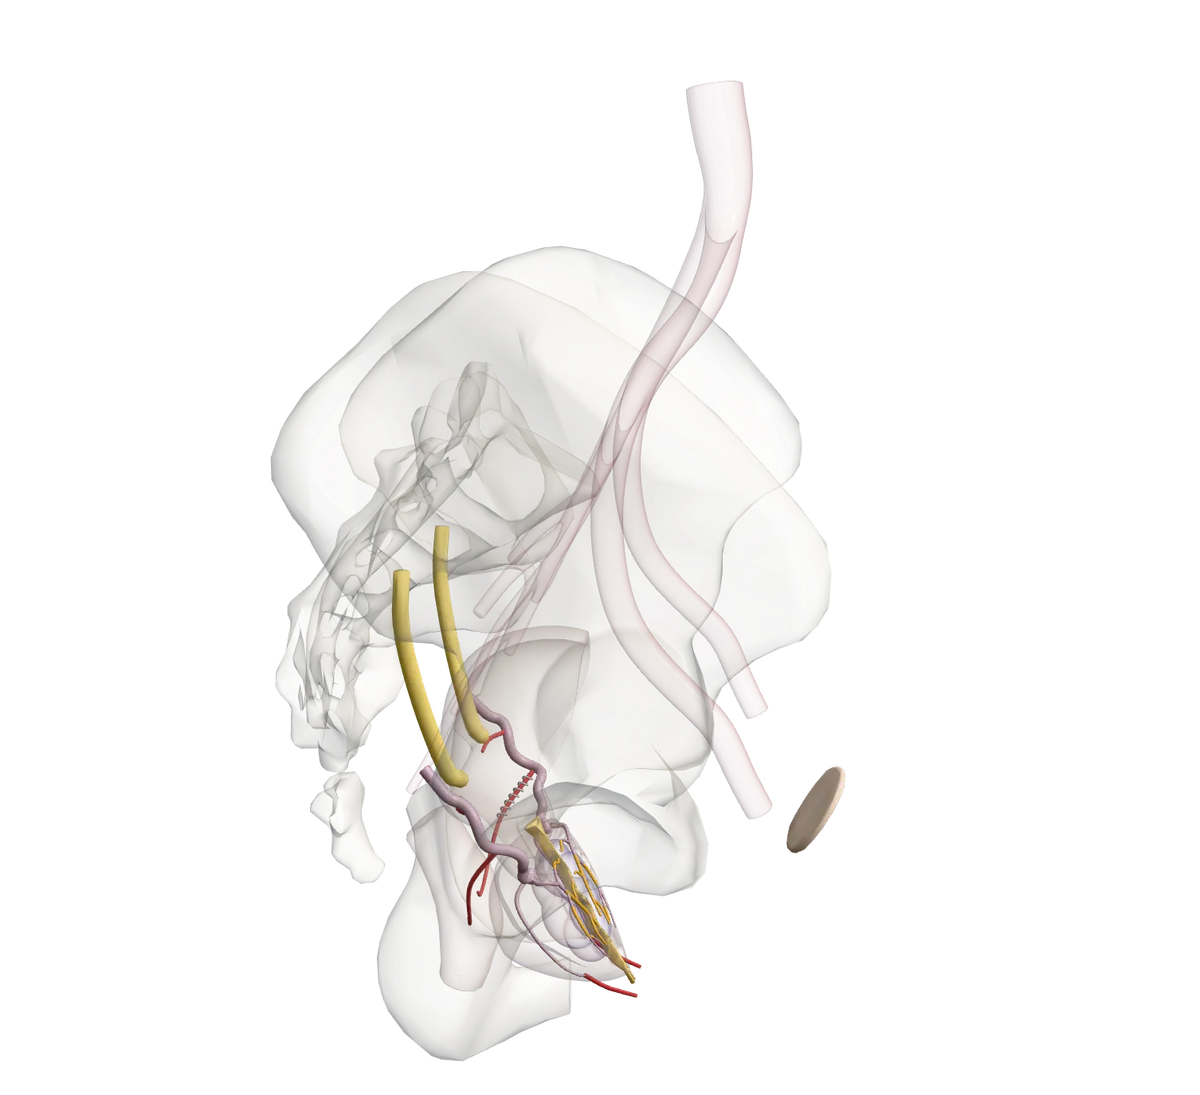
The tubes come out. The opening is closed with firm pressure or a small plug that dissolves. No stitches are needed.
You rest for a few hours afterwards. Most men go home the same day.
Good to know. The procedure usually takes 1 to 3 hours.
Afterwards
The first days can be uncomfortable
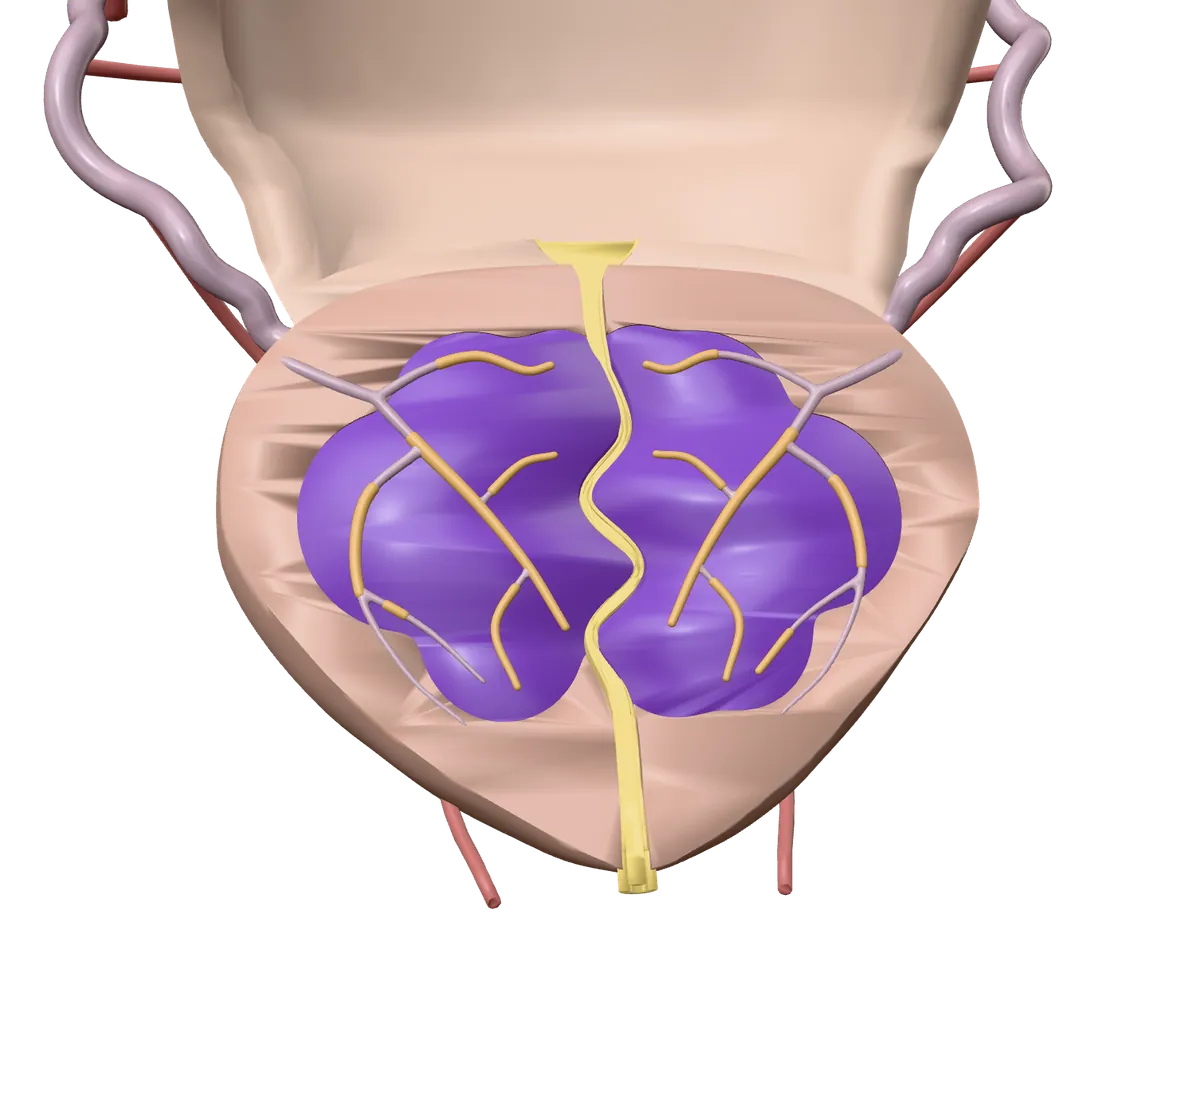
For a few days, many men have some pain low in the pelvis, burning when they pee, and a need to pee often. A little blood in the urine, semen or stool can happen too. These usually settle on their own.
Swelling can make peeing hard at first, so some men need a catheter for a short time.
Good to know. You go home with antibiotics and pain medicine. Rest for 2 to 3 days, and avoid hard exercise for about a week.
Over the next weeks, the prostate shrinks
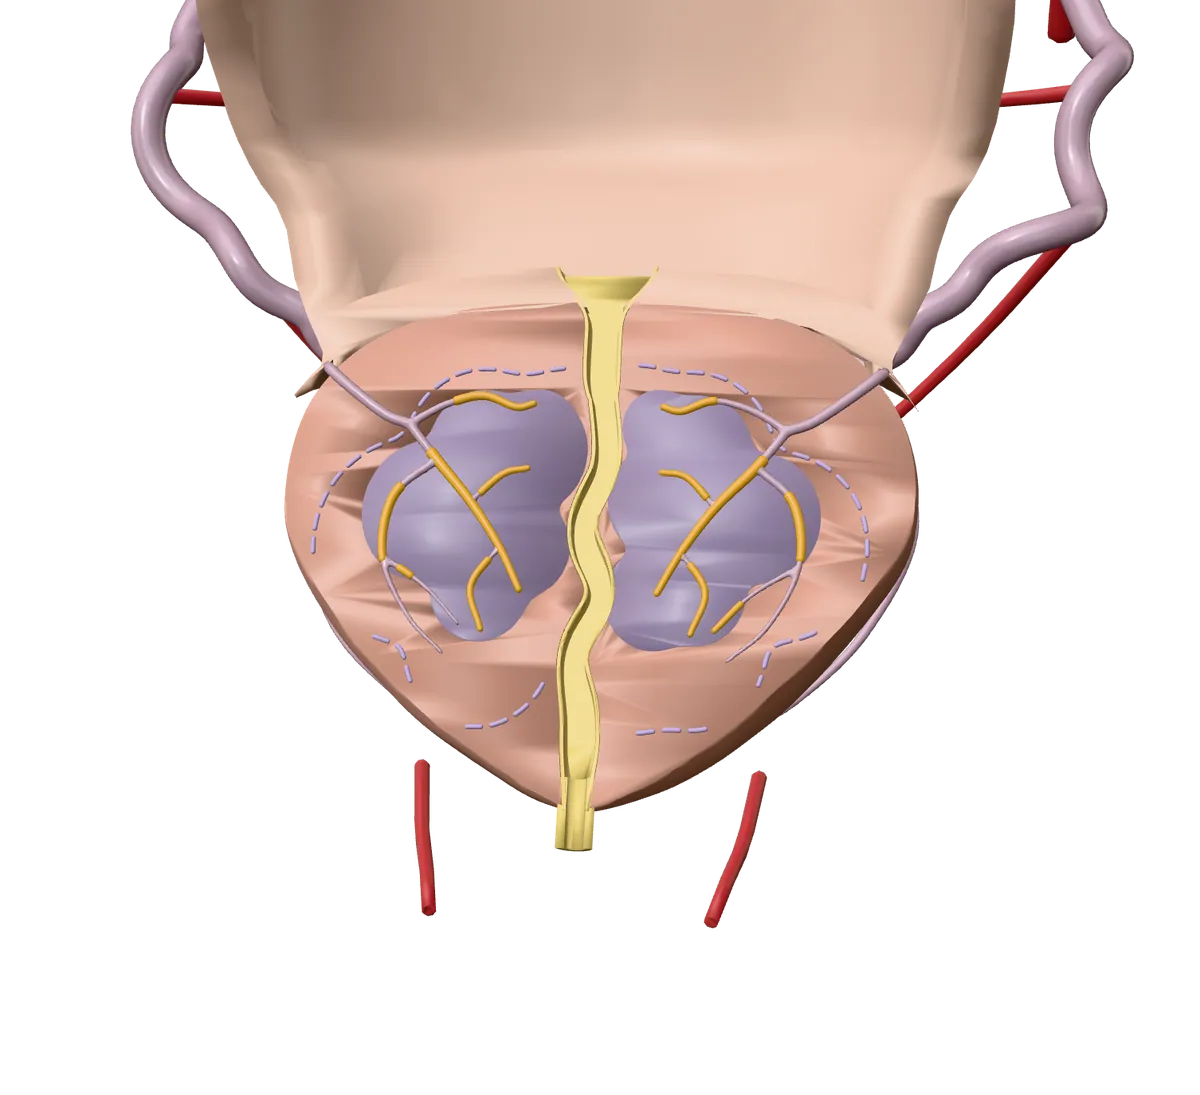
Most men find peeing gets easier within 4 to 6 weeks. In a study of 1,000 men, symptoms went from severe to mild, on average, within 3 months, and stayed mild for up to 6 years.
In the first year, the prostate often shrinks by about a quarter. Results vary. About 1 in 5 men need another treatment within 5 years.
Risks
Risks, explained plainly
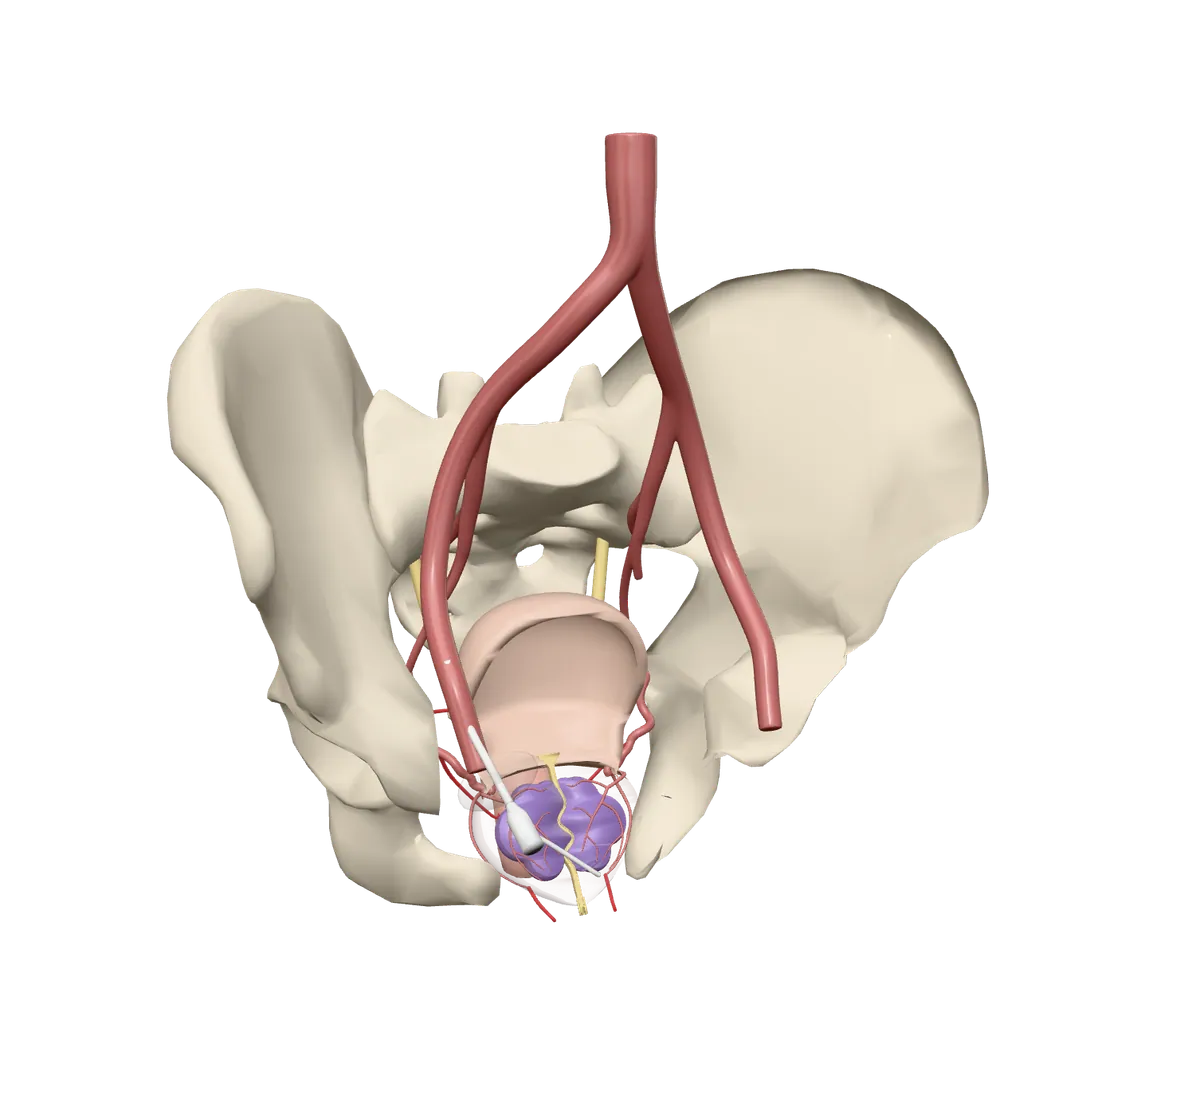
Every procedure has some risk, and most people do not have a serious problem. Each risk is listed under Benefits and risks below, with how often it happens.
Minor problems happen to about 1 in 3 men and usually pass, and serious problems happen to about 3 in 1,000.
Your visit
Before, on the day and after. Your care team’s instructions come first if they differ.
Before your procedure
Things to do. Tick them off as you go; your ticks stay on this device only.
On the day
Arrival. A nurse checks you in. A small plastic tube (IV) goes into a vein in your hand or arm for medicine. You sign a consent form, and you can still ask questions or change your mind.
Maybe a bladder catheter. Some men have a soft tube put into the bladder through the penis. It is usually taken out at the end.
Staying comfortable. You lie on your back on the X-ray table and stay awake. The skin is numbed. You can have medicine to help you relax.
The procedure. The doctor treats the arteries on both sides, often through one opening. It usually takes 1 to 3 hours.
Recovery. You rest for a few hours while nurses check you and the opening. Most men go home the same day.
Recovery
- The first hours
Rest as the nurses tell you, keeping the leg or wrist still. Some pain and cramping is common. Ask for pain medicine if you need it.
- Days 1 to 3
Rest. Take the antibiotics and pain medicine you were given. Burning when you pee, peeing often, and a little blood in your urine, semen or stool can happen. These usually settle in a few days.
- The first week
Avoid hard exercise and heavy lifting for about a week, or as your team advises. Advice differs between hospitals. Ask your team when you can drive, work and have sex.
- Weeks 1 to 2
Swelling in the prostate settles. If you went home with a catheter, it is often taken out about 2 to 4 weeks after PAE.
- Weeks 4 to 6
Most men notice that peeing is easier. The prostate keeps shrinking.
- About 3 months
Your team checks how you are doing. In a large study, symptoms were mild, on average, by 3 months.
When to get help
Call 9-1-1 now if you have
- Bleeding from the groin or wrist that does not stop after you lie down and press hard on it for 10 minutes
- Any other emergency
Call the interventional radiology (IR) team today if you have
- You cannot pee at all (this is urgent)
- A fever or chills
- Pain that gets worse instead of better
- Burning even when you are not peeing
- More blood in your urine
- Bleeding from the penis
- Sores or colour changes on the penis or scrotum
- A painful lump at the groin or wrist that keeps growing
Phone number added by the hospital before launch
If you can’t reach them, go to the nearest emergency department.
Not sure? Call HealthLink BC at 8-1-1
- You are not sure how worried to be
- You have questions about your medicines
A nurse can give health advice any time, day or night.
Call 8-1-1Deaf or hard of hearing: call 7-1-1. Translation services are available in over 130 languages.
Benefits and risks
What it can do for you
- No surgical cut. The tube goes into an artery at the groin or wrist, and nothing is cut out of the prostate.
- You stay awake. The skin is numbed, and there is no general anesthetic.
- Most men go home the same day.
- In a study of 1,000 men, symptoms went from severe to mild, on average, within 3 months, and stayed mild for up to 6 years.
- Compared with surgery through the penis (TURP), symptoms may improve about the same over 2 years, with fewer ejaculation problems. This evidence is not yet strong.
- On average, erections were not worse a year later.
- It can be an option if you cannot stop blood thinners, have a very large prostate, or need a catheter. More than 8 in 10 men with a catheter are able to stop using it.
What can go wrong
Every procedure has some risk, and most people do not have a serious problem. Each risk is listed with how often it happens. They are grouped on one scale, from very common to very rare.
Very common: more than 1 in 10 people
Pain, burning, peeing often and some blood
About half of men had some pain, in one trial. About 1 in 5 had strong pain, mostly in the first day. Up to about 17 in 100 have burning when peeing. About 12 in 100 pee more often. About 16 in 100 have blood in their semen. About 4 in 100 have blood in their urine.
As the treated prostate swells and heals, many men have pain low in the pelvis, burning when they pee, and a need to pee often for a few days. Pink or red urine, or brown or red semen, can also happen for a short time.
Changes in ejaculation or erections
Semen goes backward in 0 to 24 in 100 men, depending on the study. New erection trouble happened to 1 man in 48, in one trial.
Less fluid when you climax, or semen going backward into the bladder instead of out. Less often, trouble getting or keeping an erection. Fewer men have ejaculation problems than after surgery (TURP). On average, erections were not worse a year later.
Not working well enough
About 1 in 5 men did not count as a success at 1 year, in a large study. About 1 in 5 had another procedure within 5 years.
The prostate may not shrink enough, or symptoms may come back over time. Another treatment may be needed.
Common: 1 in 10 to 1 in 100 people
Trouble peeing
About 5 to 8 in 100 men.
Swelling can block the urethra for a while. You may need a catheter for 1 to 2 weeks while it settles. Sources differ: one patient leaflet calls this rare.
Bruise or bleeding where the tube went in
1 man in 48 (about 2 in 100) had a larger bruise, in one trial. Serious problems of any kind after PAE happen in about 3 in 1,000 men.
A small bruise is normal and fades. A larger, painful lump or bleeding is less common.
Rectal pain or blood in the stool
About 9 in 100 men have rectal pain or burning when peeing (counted together). Serious problems of any kind happen in about 3 in 1,000 men.
A sore back passage, loose stool or a little blood in the stool, usually for a short time. Much less often, beads reach the rectum and harm it.
Infection
About 3 to 4 in 100 men get a urine infection. A pocket of pus in the prostate happened to 1 in 383 men, in one study.
Fever, chills and pain can mean an infection. Most are urine infections. Less often, a pocket of pus forms in the prostate (an abscess). Antibiotics are given to lower the risk. Infection is more likely if you already had a catheter: about 5 or 6 in 100 of these men get a urine infection.
Uncommon: 1 in 100 to 1 in 1,000 people
Harm to the bladder wall
All serious problems together, including this one, happen in about 3 in 1,000 men.
Beads reaching the bladder can damage a small part of its wall. A second small procedure may be needed to remove the damaged tissue.
Harm to the penis
3 in 383 men (fewer than 1 in 100) had a sore on the penis.
Where this number comes from
3 in 383 men (fewer than 1 in 100) had a sore on the penis, in one study.
Beads reaching the arteries of the penis can cause a sore on the penis.
Other options
Questions to ask
Tick the ones you want to ask. Your ticks stay on this device only.
Check your understanding
Nothing is saved. It is just for you.
Tiny beads slow the blood flow to the prostate, so it shrinks. Nothing is cut out.
A tiny opening in an artery at the groin or wrist. The skin is numbed, and no stitches are needed.
These are common and usually settle in a few days. Call your team if they get worse instead of better.
The prostate shrinks slowly. Most men notice a change within 4 to 6 weeks.
An enlarged prostate (BPH) is not cancer. Your team may still check a PSA blood test.
Words used
- Prostate
- A small gland under the bladder that makes some of the fluid in semen.
- Enlarged prostate (BPH)
- A prostate that has grown bigger with age. It is not cancer. BPH stands for benign prostatic hyperplasia.
- Urethra
- The tube that carries pee (and semen) out of the body. It runs through the prostate.
- Embolization
- Blocking blood vessels on purpose, here with tiny beads.
- Catheter
- A thin, flexible tube. In PAE it goes into an artery. A bladder catheter is a different tube that drains pee.
- Microcatheter
- An even thinner tube that goes through the catheter into very small arteries.
- Interventional radiologist
- A doctor who treats problems through tiny openings, using X-rays or other imaging to guide them.
- Urologist
- A doctor who treats problems of the bladder, prostate and urine system.
- Urinary retention
- Not being able to empty your bladder, or not being able to pee at all.
- CT angiogram
- A CT scan with dye that makes a map of your arteries.
- PSA test
- A blood test for a protein made by the prostate. It can rise with an enlarged prostate or with cancer.
- TURP
- Surgery that removes part of the prostate through a thin tube passed up the penis.
Sources
- Society of Interventional Radiology (SIR). Enlarged prostate or benign prostatic hyperplasia (BPH) can be treated by interventional radiologists
- Society of Interventional Radiology (SIR). SIR publishes multisociety position statement on prostatic artery embolization (2019)
- Society of Interventional Radiology (SIR). Study finds prostate artery embolization to be effective long-term treatment for enlarged prostate (2023)
- Society of Interventional Radiology (SIR). Practice guidance for treatment of enlarged prostate (2026)
- Society of Interventional Radiology (SIR). AUA strengthens recommendation for PAE in new guideline (2026)
- Cardiovascular and Interventional Radiological Society of Europe (CIRSE). Embolization of the prostatic artery, patient information
- British Society of Interventional Radiology (BSIR). Prostate artery embolisation, patient information leaflet
- HealthLink BC. Benign prostatic hyperplasia (BPH)
- HealthLink BC. Enlarged prostate: should I take medicine?
- HealthLink BC. Prostate-specific antigen (PSA) test
- National Institute of Diabetes and Digestive and Kidney Diseases (US NIH). Enlarged prostate (benign prostatic hyperplasia)
- Canadian Cancer Society. What is prostate cancer? (about the prostate)
- NHS (UK). Treatment: benign prostate enlargement
- Cochrane Database of Systematic Reviews. Prostatic arterial embolization for treatment of lower urinary tract symptoms in men with benign prostatic hyperplasia (2022)
- Journal of Clinical Medicine. Prostate artery embolization: review of indications, patient selection, techniques and results (2021)
- Journal of Personalized Medicine. Prostate artery embolization: challenges, tips, tricks, and perspectives (2022)
- BMJ. Prostatic artery embolisation versus transurethral resection of the prostate: randomised, open label, non-inferiority trial (2018)
- Seminars in Interventional Radiology. Long-term PAE results: what do we know? (2022)
- CardioVascular and Interventional Radiology. Long-term outcome of prostatic artery embolization: 1072 patients over a 10-year period (2022)
- Journal of Vascular and Interventional Radiology. Meta-analysis of prostatic artery embolization for benign prostatic hyperplasia (2016)
- European Radiology. Prostate artery embolisation for benign prostatic hyperplasia: a systematic review and meta-analysis (2019)
- Journal of Vascular and Interventional Radiology. Infections after prostatic artery embolization for benign prostatic hyperplasia: an analysis of the published evidence (2026)
- Diagnostic and Interventional Imaging. Efficacy and safety of prostate artery embolization for patients with lower urinary tract symptoms and indwelling urinary catheter: a retrospective multicenter study (2022)
- HealthLink BC. HealthLink BC 8-1-1 services
About this guide
- Status
- Draft: not yet reviewed by the clinical team. The interventional radiology team will review it before it is used with patients, and the date of that review will show here.
- How it was written
- Drafted with AI writing tools from 23 published sources, then fact-checked against those sources by a separate AI check. Anything the sources did not support was taken out. The interventional radiology team will review it before it is used with patients.
- Last edited
- 14 October 2026
- Document
- Pathway P-002 · Version 0.5 · Last reviewed: not yet · Next review: 12 months after sign-off · Owner: the interventional radiology team
Was this guide clear?
Tell us if anything was hard to follow, or if something on the page looks wrong. Please do not include details about your own health. For questions about your care, contact your care team.
Both open an email to the project team. Project email: added before launch